Abstract
An 83-year-old woman presented with a 10-day history of sudden-onset diplopia in the left eye, with no preceding trauma or anticoagulant use. Initial orbital magnetic resonance imaging (MRI) on day 10 revealed a well-circumscribed retrobulbar lesion along the left inferior rectus muscle. The lesion showed heterogeneous T1 hyperintensity, low-to-intermediate T2 signal, and no definite solid enhancement, raising concern for a hemorrhagic orbital mass or neoplasm. Serial noncontrast computed tomography (CT) on days 20 and 49 showed progressive decreases in lesion size and attenuation. Follow-up MRI on day 180 confirmed complete spontaneous resolution, with no residual abnormality or underlying neoplasm. This case demonstrates that serial CT and MRI can guide safe conservative management of spontaneous retrobulbar hematoma and help avoid unnecessary surgery in clinically stable patients.
-
Keywords: Computed tomography; Hematoma; Hemorrhage; Magnetic resonance imaging; Orbit; Case reports
Introduction
Intraorbital hematoma has been associated with trauma, surgery, and systemic conditions such as coagulopathy. It may also develop secondary to underlying vascular abnormalities, including intraorbital arteriovenous or cavernous venous malformations, or to neoplasms [
1-
3]. Spontaneous intraorbital hematoma is a rare cause of an orbital mass and has been described as a hematoma, hematic cyst, hematocele, blood cyst, or “chocolate cyst” [
4-
6]. Histologically, these lesions contain blood and its degradation products, sometimes enclosed by a fibrous capsule that often lacks a true endothelial or epithelial lining [
7]. Although computed tomography (CT) and magnetic resonance imaging (MRI) frequently provide the first diagnostic clues to hemorrhagic orbital lesions, their clinical and imaging features often overlap with those of other benign and malignant orbital lesions, including cavernous venous malformations, lymphangiomas with hemorrhage, and hemorrhagic tumors. Consequently, most previously reported patients have undergone surgery for definitive diagnosis or decompression. However, the natural history of spontaneous retrobulbar hematoma has rarely been characterized, and its evolution on imaging requires further description.
We report a case of spontaneous retrobulbar hematoma that initially mimicked a hemorrhagic tumor. Serial CT and MRI guided conservative management and documented spontaneous resolution without biopsy or surgical excision. The case illustrates the potential value of short-interval follow-up imaging for distinguishing hemorrhagic orbital lesions from true neoplasms in clinically stable patients and avoiding unnecessary invasive procedures.
Case presentation
Ethics statement
Our institutional review board of Ewha Womans University seoul hospital approved this retrospective study (approval no. EMCS 2026-02-055) and waived the requirement for informed consent.
Case report
An 83-year-old woman presented with sudden-onset diplopia in the left eye that had persisted for 10 days. She had no history of head or orbital trauma, anticoagulant or antiplatelet use, diabetes mellitus, or hypertension; her only medications were inhaled treatments for long-standing asthma. She reported no Valsalva-provoking episodes before symptom onset, including severe coughing, vomiting, straining during defecation, or heavy lifting. Laboratory testing showed normal coagulation parameters: platelet count, 182×103/μL; prothrombin time, 11.5 seconds (97.5%; international normalized ratio, 1.01); and activated partial thromboplastin time, 25.4 seconds. Ophthalmologic examination showed best-corrected visual acuity of 20/20 in both eyes and no relative afferent pupillary defect. Slit-lamp examination, intraocular pressure measurements, and fundus examination were unremarkable bilaterally, with no proptosis or eyelid swelling at presentation. Automated perimetry with a Humphrey visual field analyzer identified a small inferior altitudinal defect in the left eye; the right visual field was normal. Extraocular motility testing showed limited left-eye infraduction and left hypertropia, with a mass effect around the left inferior rectus muscle. Neurologic examination identified no additional focal deficits. Orbital MRI was performed with a 3-T unit. The protocol included axial and coronal precontrast T1-weighted images (T1WI) without fat saturation, axial T2-weighted images (T2WI), coronal fat-saturated T2WI, and fat-saturated contrast-enhanced 3-dimensional T1WI. For contrast-enhanced imaging, gadobutrol was administered intravenously at 0.1 mL/kg (Gadovist 7.5 mL; Bayer Schering Pharma).
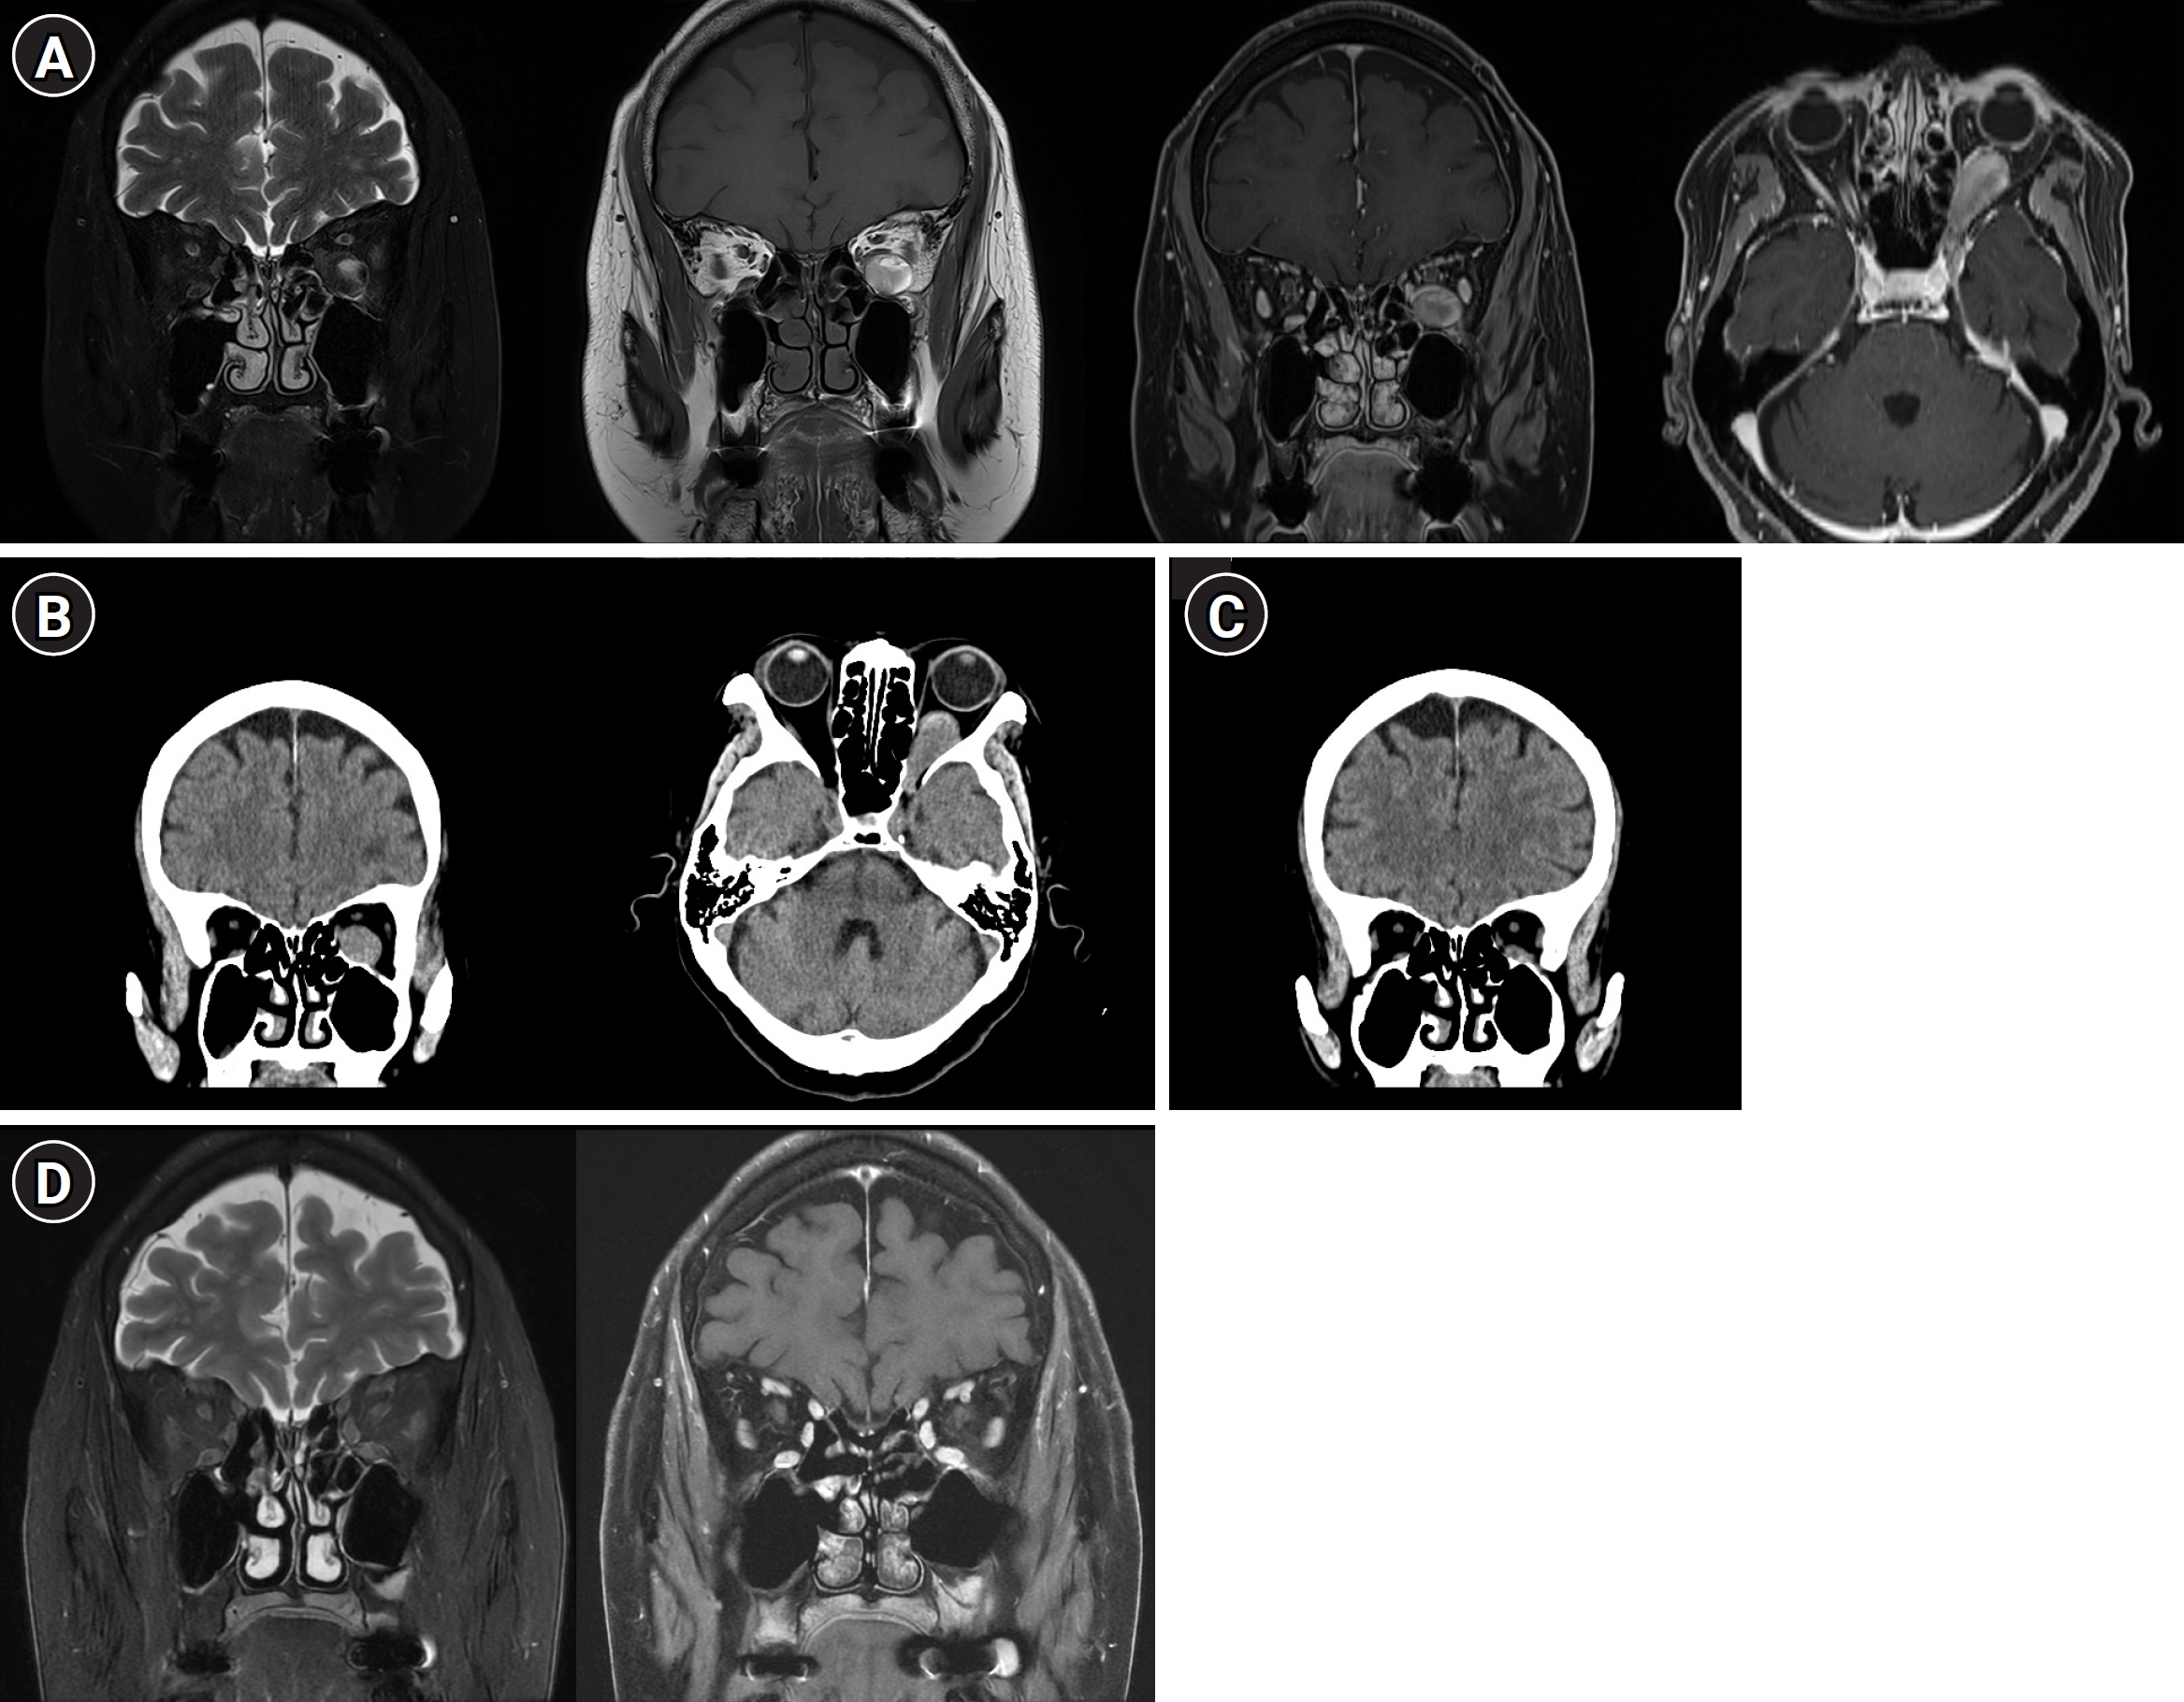
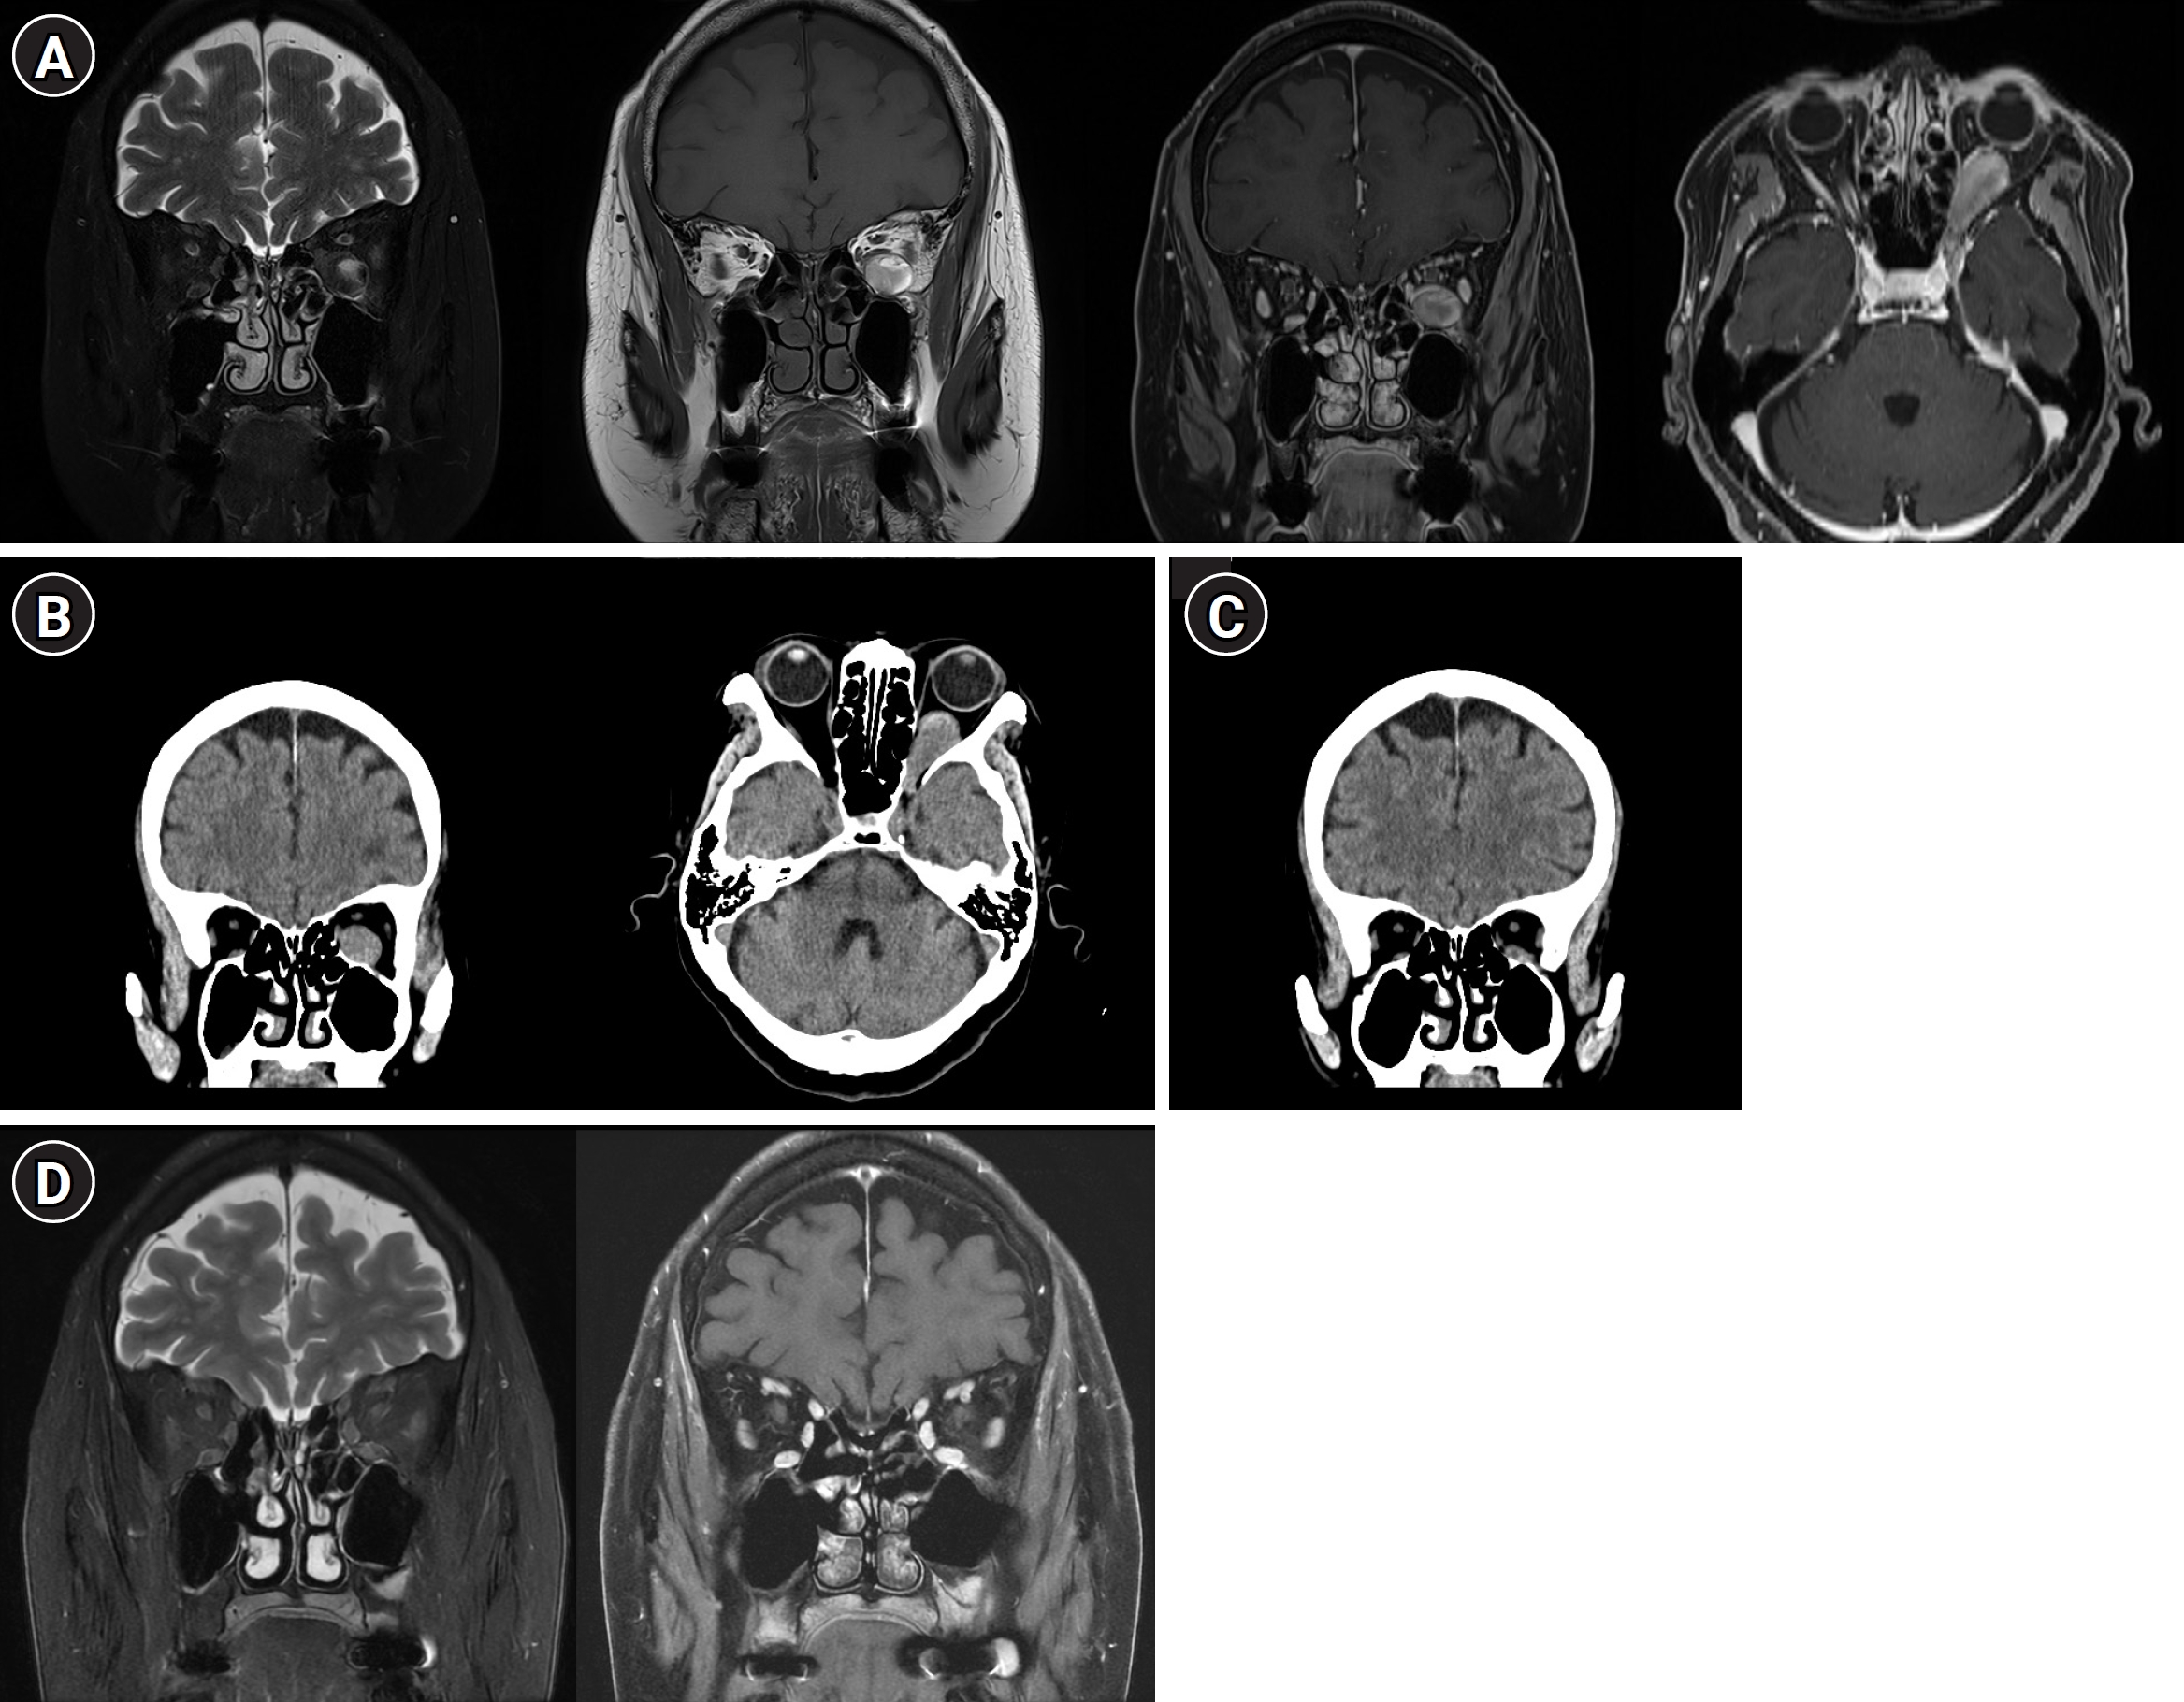
Symptom onset was designated day 0, and the hospital visit occurred on day 10. Initial MRI on day 10 showed a well-circumscribed, oval, mass-like retrobulbar lesion along the left inferior rectus muscle. The lesion had heterogeneous, predominantly low-to-intermediate signal intensity with focal very-low-signal components on T2WI and heterogeneously high signal intensity on T1WI. Contrast-enhanced 3-dimensional T1WI showed no discernible solid internal enhancement (
Fig. 1A). The T1 hyperintensity and heterogeneous low T2 signal initially favored a benign orbital mass with recent hemorrhage, such as a cavernous venous malformation or schwannoma, over a purely solid neoplasm or pure hematoma. Surgery was deferred because recent bleeding increased the risk of intraoperative hemorrhage, visual function was stable, and there was no optic nerve compression or orbital apex crowding. Conservative management with short-interval follow-up imaging was chosen.
The first follow-up noncontrast CT scan, obtained on day 20, showed the retrobulbar lesion in the same location. It was isoattenuating to the adjacent extraocular muscles and contained a small hyperdense component (
Fig. 1B). The patient reported improvement in diplopia and less restriction of ocular movement, supporting continued observation. The second follow-up CT scan, obtained on day 49, showed marked lesion shrinkage, with only a faint soft-tissue density remaining beside the inferior rectus muscle (
Fig. 1C).
Final follow-up MRI on day 180 confirmed complete lesion resolution, with no abnormal signal within or around the left inferior rectus muscle (
Fig. 1D). Diplopia had almost resolved, and repeat visual field testing showed that the inferior altitudinal defect had resolved. These findings established a diagnosis of spontaneous retrobulbar hematoma that had spontaneously resorbed rather than a hemorrhagic neoplastic lesion.
Discussion
This case illustrates how serial imaging can guide the management of hemorrhagic orbital lesions and allow selected patients to avoid invasive procedures. The evolution of the imaging findings was central to the decision to continue conservative management. CT scans obtained at day 20 and day 49 showed progressive decreases in lesion size and attenuation, and MRI at day 180 confirmed complete resolution. This course strongly favored a resolving hematoma over a hemorrhagic neoplasm. Stable visual acuity and the absence of optic nerve compression at the orbital apex further supported observation. To our knowledge, most previously reported spontaneous orbital hematomas or hematic cysts were surgically confirmed, and detailed descriptions of their natural course during conservative management remain rare.
Intraorbital biopsy and surgical exploration carry risks, particularly for hemorrhagic orbital lesions, in which tissue manipulation may provoke further bleeding. Complication rates are higher than for nonhemorrhagic orbital masses [
8,
9], and surgery may inadvertently injure the optic nerve or extraocular muscles [
10,
11]. When imaging findings are consistent with blood products and there is no urgent indication for decompression, conservative management with close clinical and radiologic surveillance may therefore be reasonable. Conversely, lesion enlargement, new solid enhancing components, or evidence of orbital apex crowding or optic nerve compromise should prompt timely surgery.
Most previous reports describe patients who underwent surgery early in their course, leaving the natural history of spontaneous retrobulbar hematoma and the optimal imaging follow-up duration incompletely characterized. Our observations suggest that these hematomas may resolve over several weeks to months, apparently taking longer than the subperiosteal hematomas described previously [
12]. Decisions about conservative management should be individualized through multidisciplinary assessment.
Hemoglobin degradation from oxyhemoglobin to deoxyhemoglobin, methemoglobin, and hemosiderin produces characteristic, stage-dependent changes in T1 and T2 signal intensity. These evolving MRI findings can help distinguish hematomas from solid vascular or neoplastic lesions [
13]. Depending on the hematoma stage, however, the signal characteristics may conceal enhancing components of an underlying neoplasm. Distinguishing cavernous venous malformations from hematomas is particularly challenging. Previous studies describe marked T2 hyperintensity with internal septations, progressive centrifugal enhancement, and low-flow vascular channels in cavernous venous malformations. These features contrast with the stage-dependent layering and absence of nodular enhancement observed in hematomas [
14,
15]. In this patient, MRI 10 days after symptom onset showed a high-signal-intensity halo surrounding a low-to-isointense component on T1WI and layers of low and high signal intensity on T2WI, without discernible nodular enhancement. CT complemented these findings by showing decreasing lesion attenuation as blood products were resorbed, providing objective evidence of hematoma resolution. Awareness of these imaging features may help radiologists when differentiation from hemorrhagic neoplasms is difficult. Serial imaging adds temporal information that can refine the differential diagnosis and guide management.
This report has several limitations. It concerns a single patient without histopathologic confirmation because the lesion resolved spontaneously during imaging follow-up. Its primary purpose, however, was to illustrate the value of short-interval follow-up imaging when initial findings do not clearly distinguish a hemorrhagic tumor from a pure hematoma and the patient has no urgent symptoms of orbital compression. The case also demonstrates that careful imaging follow-up can be a reasonable management option for such selected patients. The 6-month follow-up was insufficient to assess long-term recurrence risk. Larger studies with longer observation are needed to determine the optimal follow-up strategy and imaging predictors of spontaneous resolution.
In this case of spontaneous retrobulbar hematoma, serial CT and MRI guided safe conservative management, and the lesion resolved spontaneously without biopsy or excision. These findings support imaging follow-up to identify patients with hemorrhagic orbital lesions who may be managed conservatively and thereby avoid unnecessary surgery when appropriately selected.
-
Authors’ contribution
Conceptualization: BEL. Data curation: BEL, RGY. Formal analysis: BEL, RGY. Investigation: BEL, RGY. Methodology: BEL, RGY. Validation: BEL, RGY. Writing–original draft: RGY. Writing–review and editing: BEL, RGY.
-
Conflict of interest
No potential conflict of interest relevant to this article was reported.
-
Funding
None.
-
Data availability
Not applicable.
-
Acknowledgments
None.
-
Supplementary materials
None.
Fig. 1.Serial magnetic resonance imaging (MRI) and computed tomography (CT) findings. (A) Initial MRI on day 10. Coronal T2-weighted images (T2WI), T1-weighted images (T1WI), and contrast-enhanced coronal and axial T1WI show a well-circumscribed, mass-like retrobulbar lesion along the left inferior rectus muscle. The lesion has heterogeneous high and low signal intensity on T2WI and high signal intensity surrounding a low-to-isointense component on T1WI, without definite intralesional solid enhancement. (B) First follow-up coronal and axial CT images on day 20 show a heterogeneous iso-to-hyperdense, mass-like lesion in the left retrobulbar region. (C) Second follow-up CT on day 49 shows a marked decrease in lesion size. (D) Final MRI on day 180. Coronal T2WI and contrast-enhanced T1WI show complete lesion resolution, with no abnormal signal within or around the left inferior rectus muscle.
References
- 1. Husag L, Krauer W, Probst C. Spontaneous intraorbital hematoma. Schweiz Arch Neurol Neurochir Psychiatr 1978;122:187-203.
- 2. Martinez Devesa P. Spontaneous orbital haematoma. J Laryngol Otol 2002;116:960-961. https://doi.org/10.1258/00222150260369552
- 3. Yamashita T, Hosoda H, Shinonaga M, Fujitsu K, Kuwabara T. Unilateral exophthalmos caused by organized hematoma of the orbit: report of a case (author’s transl). No Shinkei Geka 1978;6:185-189.
- 4. Ali HM, Khairallah AS, Moghazy K. Acute spontaneous extraconal hematic cyst of the orbit. Saudi J Ophthalmol 2011;25:85-88. https://doi.org/10.1016/j.sjopt.2010.11.003
- 5. Amrith S, Baratham G, Khoo CY, Low CH, Sinniah R. Spontaneous hematic cysts of the orbit presenting with acute proptosis: a report of three cases. Ophthalmic Plast Reconstr Surg 1990;6:273-277. https://doi.org/10.1097/00002341-199012000-00009
- 6. Sullivan TJ, Wright JE. Non-traumatic orbital haemorrhage. Clin Exp Ophthalmol 2000;28:26-31. https://doi.org/10.1046/j.1442-9071.2000.00241.x
- 7. Yoshikawa K, Fujisawa H, Kajiwara K, Fujii M, Kato S, Akimura T, Nomura S, Gondo T, Suzuki M. Cause of hematic cysts of the orbit: increased fibrinolysis and immunohistologic expression of tissue plasminogen activator. Ophthalmology 2009;116:130-134. https://doi.org/10.1016/j.ophtha.2008.08.041
- 8. Liu D. Complications of fine needle aspiration biopsy of the orbit. Ophthalmology 1985;92:1768-1771. https://doi.org/10.1016/s0161-6420(85)34106-4
- 9. Ting DS, Perez-Lopez M, Chew NJ, Clarke L, Dickinson AJ, Neoh C. A 10-year review of orbital biopsy: the Newcastle Eye Centre Study. Eye (Lond) 2015;29:1162-1166. https://doi.org/10.1038/eye.2015.95
- 10. Bonavolontà G. Postoperative blindness following orbital surgery. Orbit 2005;24:195-200. https://doi.org/10.1080/01676830500192092
- 11. Gowda A, Tong JY, Selva D. Ocular hypotony after extraocular muscle biopsy for a patient with orbital myositis. Ophthalmic Plast Reconstr Surg 2023;39:516-517. https://doi.org/10.1097/IOP.0000000000002397
- 12. Usmani E, Shapira Y, Patel S, Psaltis AJ, Selva D. Case report: late spontaneous orbital subperiosteal hematoma after endoscopic sinonasal tumor resection. Int J Surg Case Rep 2023;104:107954. https://doi.org/10.1016/j.ijscr.2023.107954
- 13. Alkatan HM, Al Otaibi M, Maktabi AM, Aljaedi H, Elkhamary SM, Al-Faky Y, Alsuhaibani AH. Clinical, radiological and histopathological characteristics of surgically removed orbital hematic cysts: a case series. Saudi J Ophthalmol 2018;32:45-51. https://doi.org/10.1016/j.sjopt.2018.04.002
- 14. Yap UJ, Chung SR, Lee JH, Sa HS. Clinicoradiologic differences between orbital schwannoma and cavernous venous malformation: a retrospective comparative case series. Sci Rep 2025;15:39743. https://doi.org/10.1038/s41598-025-05345-x
- 15. Zhang L, Li X, Tang F, Gan L, Wei X. Diagnostic imaging methods and comparative analysis of orbital cavernous hemangioma. Front Oncol 2020;10:577452. https://doi.org/10.3389/fonc.2020.577452
Citations
Citations to this article as recorded by