Abstract
-
Purpose
Clinical fieldwork in genetic counseling education is constrained by limited training sites, shortages of clinical supervisors, and administrative burdens. Simulation-based learning, including role-play, has therefore been used to support development of counseling competencies. This study described the development, implementation, operational structure, and feasibility of a role-play-based practicum in a graduate genetic counseling program.
-
Methods
This retrospective descriptive report was based on Genetic Counseling Practicum, a spring 2024 course for 11 third-semester students in a graduate genetic counseling program in South Korea. Twenty-two role-play scenarios were developed, including 11 hereditary cancer cases and 11 pediatric or adult genetic disorder cases. The scenarios simulated pretest and posttest encounters during a 6-week, 2-block practicum. Students alternated between counselor and counselee roles, recorded sessions outside class time, and received domain-guided peer and faculty feedback.
-
Results
The scenarios covered patient ages from infancy to late adulthood and included somatic and germline pathogenic variants, a negative multigene panel result, and chromosomal or epigenetic abnormalities. All 22 planned sessions were completed and recorded as scheduled, and all 11 students completed their assigned sessions. The planned assignment, recording, review, and feedback procedures were completed without documented omissions. Approximately 11 scheduled class hours were devoted to feedback, and no external clinical sites or supervisors were required.
-
Conclusion
This study presents an operationally feasible model for a role-play-based practicum with diverse scenarios in a graduate genetic counseling curriculum. It may serve as a practical reference for programs considering similar simulation-based training.
-
Keywords: Genetic counseling; Education; Role-play; Feedback
Introduction
Advances in the diagnosis and treatment of genetic disorders and hereditary cancers have made genetic counseling an increasingly important component of patient care [
1-
5]. Genetic counseling helps individuals and families understand and adapt to the medical, psychological, and familial implications of genetic contributions to disease [
6]. The process includes risk assessment through interpretation of family and medical histories, education about inheritance and management, and support for informed decision-making [
6].
The National Society of Genetic Counselors and the Accreditation Council for Genetic Counseling have identified core competencies for genetic counseling, including professional knowledge, counseling skills, ethical judgment, and patient-centered communication [
7,
8]. These organizations’ competency frameworks emphasize that genetic counselors are not only providers of medical information, but also healthcare professionals who address patients’ emotional needs and help navigate ethical dilemmas [
6,
9]. Recent studies have also described competency checklists and self-efficacy measures relevant to the counseling process [
10,
11]. Because these competencies are difficult to cultivate through theoretical learning alone, genetic counseling programs need practice-based education that allows students to encounter diverse clinical situations repeatedly [
12].
In practice, however, clinical training opportunities are limited by shortages of training institutions and qualified clinical supervisors, as well as by administrative burdens [
13,
14]. To address these constraints, the Accreditation Council for Genetic Counseling has allowed standardized patient and simulation sessions that meet specified criteria to count toward the participatory cases required for graduation [
15,
16].
Role-play is widely used in medical education to simulate clinical encounters and connect theoretical knowledge with practical skills [
17]. In genetic counseling education, role-play may help strengthen communication skills and empathetic responsiveness by requiring learners to perform both counselor and counselee roles [
18]. In South Korea, however, genetic counseling remains a relatively new formal discipline; graduate training programs and professional accreditation systems have been established only within the past decade [
19]. Reports describing how role-play-based training is implemented within Korean genetic counseling programs remain scarce.
Therefore, this study aimed to describe the structure and operational procedures of a role-play-based practicum conducted within the regular curriculum of the graduate genetic counseling program at Ewha Womans University and to present an educational model for implementing role-play-based training in genetic counseling education.
Methods
Study design
This retrospective descriptive educational report examined the development, implementation, and operational feasibility of a role-play-based practicum within the regular curriculum of the graduate genetic counseling program at Ewha Womans University College of Medicine.
Educational setting and participants
The practicum was offered as the course “Genetic Counseling Practicum” during the spring 2024 semester (March–June) to 11 third-semester students. Three faculty members supervised the course by reviewing recorded sessions and providing feedback throughout the semester. In the first semester, students completed theoretical coursework in genetic counseling. In the second semester, they participated in role-play exercises in which the instructor served as the counselee and the student served as the counselor. These introductory activities focused mainly on brief explanations of inheritance patterns and genetic testing. The third-semester practicum extended this earlier training by requiring students to conduct more complete counseling encounters, respond to counselee presentations, observe peer performance, and experience both counselor and counselee roles.
Development of role-play scenarios
A total of 22 scenarios were developed to represent clinical situations encountered in genetic counseling practice: 11 hereditary cancer cases and 11 cases involving pediatric or adult genetic disorders (
Table 1). Each scenario simulated either a pretest or posttest counseling session and included clinical background information needed for counseling, such as the patient’s clinical presentation, family history, and genetic testing context (
Table 2).
The scenarios were designed to maintain comparable difficulty within each category so that assigned cases would be reasonably equitable across students. In addition to typical genetic counseling situations, some scenarios included ethical or social issues or more challenging communication contexts.
Practicum structure and role assignment
The practicum was conducted over 6 weeks and organized into two 3-week blocks. Hereditary cancer scenarios were implemented during the first block, followed by pediatric or adult genetic disorder scenarios during the second block. This sequence was selected because hereditary cancer scenarios followed a more standardized counseling structure, whereas pediatric or adult genetic disorder scenarios involved more heterogeneous phenotypes and counseling contexts. Within each 3-week block, sessions were distributed across the weeks in a 4-4-3 pattern, for a total of 22 sessions.
Two weeks before the practicum began, students received the full list of role-play scenarios. Counselor assignments were based on students’ individual case preferences, whereas counselee roles were determined by drawing lots. Because these assignment processes were independent, student pairings varied across sessions and between the hereditary cancer and pediatric or adult genetic disorder blocks rather than following a deliberately rotated pairing design. Faculty members provided patient-specific instructions individually to the students assigned to the counselee role 1 week before each session by e-mail or messenger. As a result, students assigned to the counselor role had no advance knowledge of the counselee’s specific presentation.
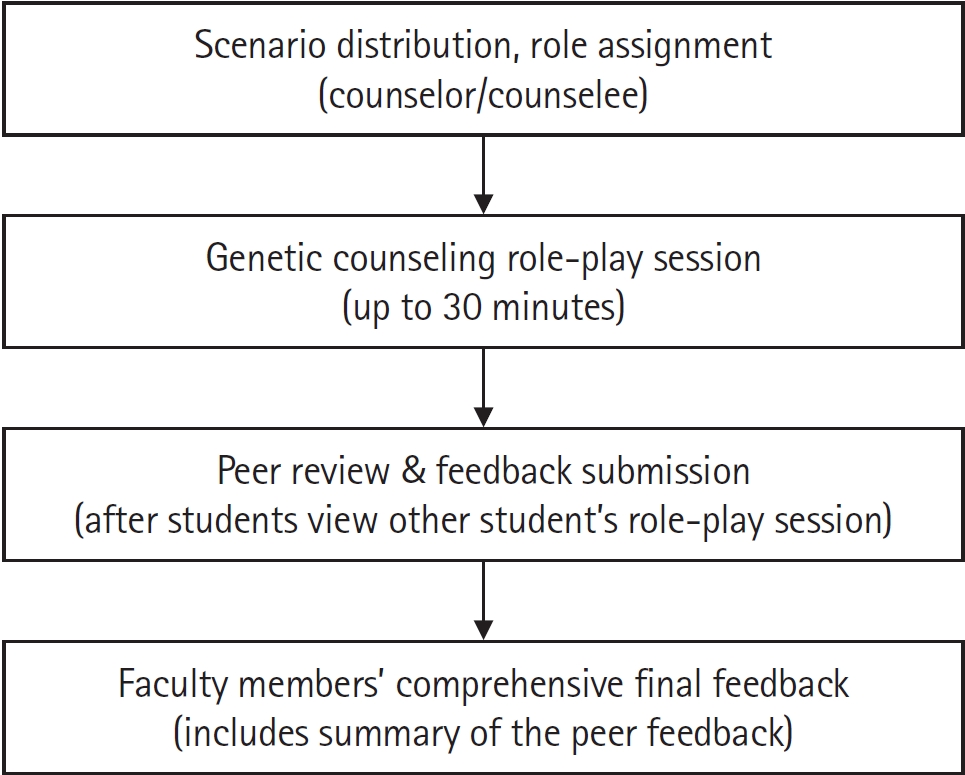
Each role-play session was conducted outside scheduled class time by a pair of students within the assigned time frame and was recorded by the participating students. Students alternated between counselor and counselee roles; each student participated twice as a counselor and twice as a counselee during the practicum. This role-rotation structure was intended to allow students to experience both provider and patient perspectives within the genetic counseling process. Each session was scheduled for up to 30 minutes, with extensions permitted as needed to preserve the natural flow of the counseling encounter; no strict time limit was enforced. Recordings were uploaded to a shared cloud platform, where faculty members and peer students could review them before the corresponding class session and prepare feedback. The recordings were deleted after each class session and were not retained. The overall practicum workflow is summarized in
Fig. 1.
No standardized feedback instrument, such as a fixed checklist or rating form, was used. Instead, feedback was provided in a narrative, individualized format guided by common domains: communication strategies, delivery of genetic information, empathy and responsiveness, strengths of the counseling process, and areas for improvement. Faculty members and peers reviewed the recorded sessions before the corresponding class and prepared feedback tailored to the clinical background and counseling context of each scenario (
Table 2).
Class time was devoted exclusively to feedback, with approximately 30 minutes allotted to each session. Faculty members and observing peers provided comments, while the students who had performed the counselor and counselee roles reflected on their experiences and considered questions that could have been explored further from the patient’s perspective. Faculty feedback synthesized key observations raised by peers and provided additional guidance on adapting communication strategies and explanations to the disease context and counseling situation.
Assessment of operational feasibility
For this retrospective report, operational feasibility was characterized descriptively using aggregate course records and scheduling information available at the time of manuscript preparation. The examined indicators were completion of the planned role-play sessions; adherence to the 6-week schedule, 2-block sequence, and planned role assignments; completion of session recording, upload, advance review, and feedback; scheduled class time required for feedback; and need for external clinical training sites or external supervisors. Feasibility thresholds were not defined prospectively, and no validated implementation measure was used. Student acceptability and educational effectiveness were outside the scope of this report.
Ethical considerations
This study described the structure and operational procedures of a regular graduate-level course in the Genetic Counseling Program. No identifiable personal information or individual-level student data were collected or analyzed. The role-play recordings used for feedback preparation were deleted after each class session and were not retained beyond the practicum. Because the study was a retrospective descriptive report of a completed course, review by the Institutional Review Board (IRB) was sought after the practicum had ended, at the time of manuscript preparation. The IRB of Ewha Womans University reviewed the study and determined that it was exempt from IRB review (IRB no. 2026-0078).
Results
The 22 scenarios covered patient ages from infancy to late adulthood and included both pretest and posttest counseling situations within each category (
Table 1). The hereditary cancer scenarios included diverse variant and test-result types, including somatic and germline pathogenic variants and a negative multigene panel result. The pediatric or adult genetic disorder scenarios included classic single-gene conditions as well as chromosomal or epigenetic abnormalities, representing a range of clinical situations encountered in genetic counseling practice.
All 22 planned role-play sessions were completed and recorded during the scheduled 6-week practicum, and all 11 students completed their assigned sessions. The planned assignment, recording, review, and feedback procedures were completed for all 22 sessions. Approximately 11 scheduled class hours were devoted to feedback across the 22 sessions. Faculty and peer feedback was provided for every session, and no session was omitted from the feedback process. The practicum did not require external clinical training sites or external supervisors. Time spent by faculty members and students reviewing recordings outside class was not systematically measured.
Discussion
This study described the structure and implementation of a student-led, role-play-based practicum conducted within a graduate genetic counseling program and presented an operational model used in an actual training setting. Genetic counseling requires more than the delivery of medical information; it also requires effective communication, empathetic responses, and ethical decision-making that accounts for patients’ individual circumstances and values. These competencies are widely recognized as core components of genetic counseling practice [
7-
9]. Because such competencies are difficult to develop through theoretical instruction alone, health professional education has increasingly emphasized practice-based approaches that allow students to engage in simulated counseling situations [
12,
15,
16,
20-
23]. The practicum described in this study incorporated repeated participation in simulated counseling encounters, rotation between counselor and counselee roles, and domain-guided feedback, thereby creating opportunities for experiential and reflective learning.
In this practicum, students alternated between counselor and counselee roles, with the counselee role assigned as frequently as the counselor role. This design treated the patient perspective as a central component of training rather than as a secondary activity. Beyond practicing counseling delivery, students were expected to consider how patients receive, interpret, and respond to information during counseling encounters. This experience may help future counselors judge which information to emphasize, which details to condense, and how to communicate in a patient-centered manner [
24-
28]. Previous studies have similarly reported that role-switching activities in medical and communication training can promote empathy and improve understanding of patient perspectives [
27,
28].
Another important aspect of this practicum was the use of role-play scenarios that represented a wide range of counseling situations, including ethical or social issues as well as more typical counseling contexts. This broad scenario set exposed students to situations that may arise in actual genetic counseling practice. Case-based learning with such scenarios allows students to anticipate and practice counseling strategies for varied clinical situations that may occur in real-world practice [
18,
21,
24]. Genetic counseling involves complex interactions shaped by disease characteristics, family relationships, and patients’ personal values [
6,
9]. Exposure to diverse scenarios may therefore help students develop flexible counseling approaches that can be adapted to different clinical situations [
29].
A distinctive feature of the practicum was its combination of peer feedback, faculty feedback, and student self-reflection. Students reviewed recordings of their peers’ role-play sessions and provided peer feedback, while students who had performed the counselor and counselee roles reflected on their own experiences. This combination of peer observation, external feedback, and self-reflection encouraged students to review their counseling performance from multiple perspectives and to identify potential areas for improvement through reflective learning [
30-
33].
Faculty feedback was another key educational component of the practicum. Faculty members reviewed the recorded role-play sessions and peer feedback and then provided domain-guided feedback focused on competencies required in genetic counseling practice. These competencies included communication strategies, delivery of genetic information, empathetic responses, and explanation of genetic information in relation to the disease context and counseling situation. Previous studies have emphasized that feedback is a critical component of simulation-based education because it facilitates reflective learning and supports clinical skill development [
30,
32-
34]. Similarly, the educational structure implemented in this practicum brought together role-play participation, peer observation, and faculty feedback as mutually reinforcing components of reflective learning.
This study contributes to the literature by systematically describing the structure and implementation of a role-play-based practicum conducted within an actual graduate genetic counseling curriculum. Reports describing the operational structure of role-play-based training programs in genetic counseling education remain limited. The present study therefore provides a practical example of how such sessions can be organized within a genetic counseling training program, including scenario sequencing, session scheduling, role assignment, recording procedures, and the use of feedback sessions to accommodate limited class time. Given ongoing constraints on clinical placement opportunities and supervision resources in genetic counseling education, this operational model may help programs plan simulation-based learning within their available resources.
This study has several limitations. First, it was a retrospective descriptive report of a single course conducted within 1 graduate program and 1 student cohort, which limits its generalizability to programs with different curricular structures, cohort sizes, or faculty resources. Second, operational feasibility was characterized retrospectively from available course records rather than assessed using prospectively defined criteria or a validated implementation measure. Third, faculty preparation time, student workload outside class, technical difficulties, and administrative burden were not systematically measured. Fourth, student acceptability, satisfaction, and educational outcomes, including changes in counseling knowledge, communication skills, empathy, or clinical competence, were not evaluated qualitatively or quantitatively. Finally, implementation across multiple cohorts and the long-term sustainability of the model remain unknown. Future studies should incorporate structured measures of educational outcomes, participant experience, resource use, and implementation outcomes in different training settings.
In conclusion, this study presents a detailed operational example of a role-play-based practicum implemented within a graduate genetic counseling curriculum. The model combined diverse counseling scenarios, equal rotation between counselor and counselee roles, recorded peer observation, self-reflection, and faculty feedback without requiring external clinical training sites. Although educational effectiveness, acceptability, and long-term sustainability were not evaluated, the operational structure and practical considerations described here may provide a starting point for programs designing simulation-based training within their available resources.
-
Authors’ contribution
Conception and design: AK, JH. Curriculum analysis: SAL, MSP. Writing–original draft: SAL. Writing–review & editing: AK, JH. Final approval of the version to be published: AK, JH.
-
Conflict of interest
No potential conflict of interest relevant to this article was reported.
-
Funding
None.
-
Data availability
Not applicable.
-
Acknowledgments
None.
-
Supplementary materials
None.
Fig. 1.Workflow for role-play implementation.
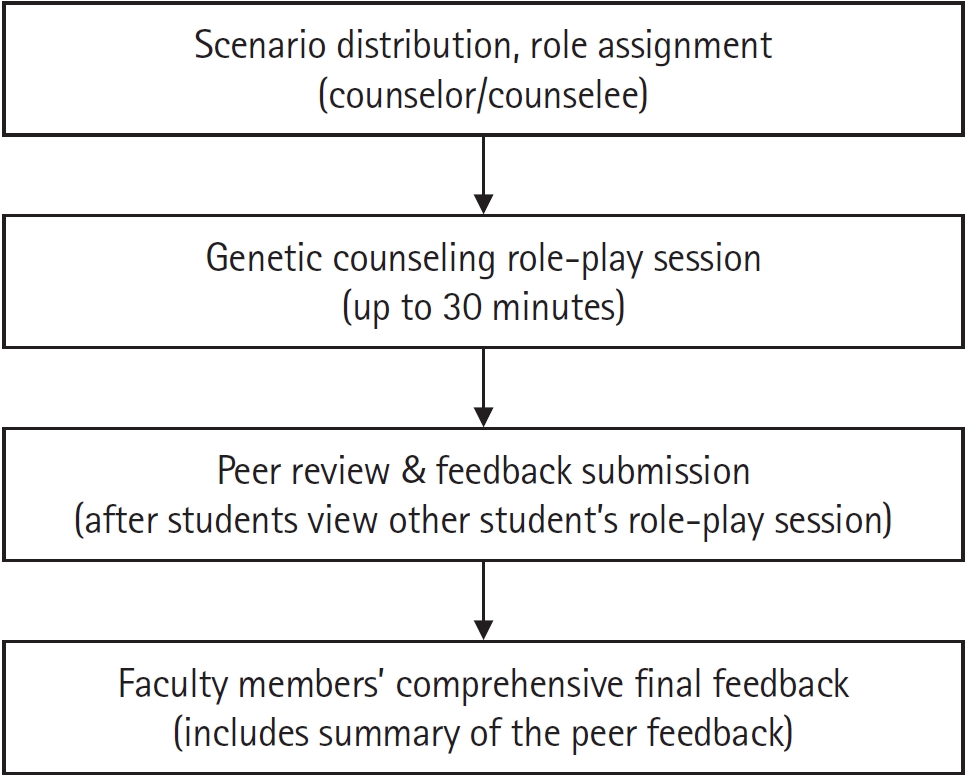
Table 1.Summary of genetic counseling role-play case scenarios
|
Category |
Case no. |
Summary |
|
Hereditary cancer |
Case 1 |
Pretest counseling for a 59-year-old woman with stage IV lung adenocarcinoma in whom a somatic BRCA2 variant had been identified. |
|
Case 2 |
Pretest counseling for a 52-year-old man with a family history of breast cancer. |
|
Case 3 |
Pretest counseling for a 35-year-old woman with hereditary breast cancer and a family history of a TP53 pathogenic variant. |
|
Case 4 |
Pretest counseling for a 35-year-old woman with a family history of gastric and breast cancer to evaluate the possibility of hereditary diffuse gastric cancer syndrome. |
|
Case 5 |
Posttest counseling for a 33-year-old woman with breast cancer, a family history of multiple cancers, and negative multigene panel testing results. |
|
Case 6 |
Posttest counseling for a 78-year-old woman with metastatic triple-negative breast cancer in whom a somatic BRCA1 variant had been identified and whose family history further suggested hereditary cancer. |
|
Case 7 |
Pretest counseling for a 45-year-old man with colorectal cancer and a family history of colorectal cancer to evaluate the possibility of Lynch syndrome. |
|
Case 8 |
Pretest counseling for a 28-year-old man with a clinical diagnosis of familial adenomatous polyposis. |
|
Case 9 |
Posttest counseling for a 54-year-old man with multiple colorectal adenomas and an identified heterozygous MUTYH variant. |
|
Case 10 |
Posttest counseling for a 40-year-old woman with renal cell carcinoma, pheochromocytoma, and an identified pathogenic VHL variant. |
|
Case 11 |
Posttest counseling for the family of a 15-month-old boy with retinoblastoma and an identified pathogenic RB1 variant. |
|
Pediatric/adult genetic disorders |
Case 1 |
Pretest counseling for a 5-year-old boy with autism spectrum disorder and developmental delay. |
|
Case 2 |
Pretest counseling for a 20-year-old woman with muscle weakness and a family history of similar symptoms to evaluate possible carrier status for Duchenne muscular dystrophy. |
|
Case 3 |
Pretest counseling for a 29-year-old woman with suspected Charcot–Marie–Tooth disease type 1A. |
|
Case 4 |
Pretest counseling for a 14-year-old boy with suspected Marfan syndrome. |
|
Case 5 |
Pretest counseling for a 2-year-old girl with rib fractures and pneumothorax to evaluate possible skeletal dysplasia. |
|
Case 6 |
Pretest counseling for a 37-year-old man with a family history of Parkinson disease. |
|
Case 7 |
Pretest counseling for an 18-month-old girl with craniofacial anomalies and a high-arched palate to evaluate possible Crouzon syndrome. |
|
Case 8 |
Posttest counseling for a newborn with characteristic facial features and cry and an identified 5p deletion consistent with cri-du-chat syndrome. |
|
Case 9 |
Posttest counseling for a 6-month-old boy with overgrowth, macroglossia, and an identified DNA methylation abnormality consistent with Beckwith–Wiedemann syndrome. |
|
Case 10 |
Posttest counseling for a 16-year-old girl presenting with amenorrhea and identified compound heterozygous CYP21A2 variants consistent with 21-hydroxylase–deficient congenital adrenal hyperplasia. |
|
Case 11 |
Posttest counseling for a 25-month-old girl with recurrent fractures, blue sclera, and an identified COL1A1 variant consistent with osteogenesis imperfecta. |
Table 2.Representative case scenarios and patient instructions for hereditary cancer and pediatric genetic disorder cases
|
Scenario |
Patient role guidance |
|
Hereditary cancer: pretest counseling |
A 45-year-old man was recently diagnosed with colorectal cancer and referred to the cancer center. The referral letter indicated that multiple family members had colorectal cancer. Given his young age at diagnosis, Lynch syndrome was suspected. IHC analysis of the colorectal tumor demonstrated normal expression of MLH1, MSH2, MSH6, and PMS2 proteins. The counseling session addressed family history, personal medical history, the possibility of Lynch syndrome, testing options, and follow-up management depending on the results. |
• Patient issue: The patient developed colorectal cancer at a young age and, given the family history, is concerned about the possibility of cancer in his children. The patient has 2 children: a 10-year-old son and a 12-year-old daughter. |
|
Counseling should include discussion of Lynch syndrome risk based on the combination of family history and IHC findings. |
• Family history: Both parents are alive in their mid-70s and have no history of cancer. The paternal grandmother was diagnosed with colorectal cancer in her 70s, was treated successfully, and died of natural causes in her late 80s. The paternal great-grandfather also had colorectal cancer, with an estimated age at onset in his 60s; he died in his mid-60s. No other family history of cancer was reported. |
|
Pediatric genetic disorders: posttest counseling |
A 6-month-old boy presented with macrosomia, macroglossia, diastasis recti, an ear pit, and advanced bone age corresponding to 9 months at 6 months of chronological age. Beckwith–Wiedemann syndrome was suspected. DNA methylation testing of the 11p15.5 region revealed loss of methylation at IC2 on the maternal allele. The session was conducted as posttest counseling. The parents initially understood the test to be a genetic sequencing test and did not realize that it was a methylation assay. |
• Clinical course: The child was noted to be large at birth with macroglossia, for which genetic testing was recommended and performed. |
|
• Pregnancy history: Natural conception, G3P1, with 1 early miscarriage. At 2–3 weeks’ gestation, the mother underwent a dental X-ray, which the physician explained was harmless. Prenatal ultrasounds showed no abnormalities, but from 20 weeks’ gestation, the fetus measured larger than expected for gestational age. Noninvasive prenatal testing yielded normal results; amniocentesis was not performed. |
|
• Birth history: The child was delivered by cesarean section when the mother was 36 years old and the father was 39 years old. Birth weight was 4.4 kg, and birth length was 53 cm. |
|
• Development: The child achieved head control at 2.5 months and rolled over at 3–4 months; he is currently able to sit briefly for 2–3 seconds. The child is cared for at home. |
|
• Physical findings: Height and weight are both above the 99th percentile. Radiographic bone age is consistent with 9 months. Diastasis recti is under observation. An ear pit is present and is also seen in the mother. |
|
• Family history: No additional notable findings were reported. |
References
- 1. Culver JO, Bertsch NL, Kurz RN, Cheng LL, Pritzlaff M, Rao SK, Stasi SM, Stave CD, Sharaf RN. Systematic evidence review and meta-analysis of outcomes associated with cancer genetic counseling. Genet Med 2024;26:100980. https://doi.org/10.1016/j.gim.2023.100980
- 2. Lee HJ. Raising awareness of genetic diseases and personalized genomic medicine. J Korean Soc Wellness 2022;17:79-85. https://doi.org/10.21097/ksw.2022.2.17.1.79
- 3. Lee SA, Park S, So MK, Chung HS, Kim HS, Kim A, Huh J. What kind of information is requested by patients and families with genetic disorders? : the analysis of an online patient community in South Korea. J Community Genet 2025;16:787-797. https://doi.org/10.1007/s12687-025-00827-x
- 4. Manickam K, McClain MR, Demmer LA, Biswas S, Kearney HM, Malinowski J, Massingham LJ, Miller D, Yu TW, Hisama FM; ACMG Board of Directors. Exome and genome sequencing for pediatric patients with congenital anomalies or intellectual disability: an evidence-based clinical guideline of the American College of Medical Genetics and Genomics (ACMG). Genet Med 2021;23:2029-2037. https://doi.org/10.1038/s41436-021-01242-6
- 5. Seo SH, Kim N, Yoo J, Kim DH, Kim J, Huh J, Kong SY, Seo EJ; Committee of Genetic Counseling in Korean Society for Genetic Diagnostics (KSGD). Issues, challenges, and future perspectives of genetic counseling in Republic of Korea: perspectives of laboratory physicians based on a 2022 survey. J Genet Couns 2024;33:1351-1357. https://doi.org/10.1002/jgc4.1863
- 6. Korean Society of Medical Genetics and Genomics. Genetic counseling. Rev. ed. Daniel Publishing; 2022.
- 7. National Society of Genetic Counselors. Exploring the scopes of three genetic counseling organizations in North America [Internet]. National Society of Genetic Counseling; 2025 [cited 2026 Jan 1]. Available from: https://perspectives.nsgc.org/Article/exploring-the-scopes-of-three-genetic-counseling-organizations-in-north-america
- 8. Accreditation Council for Genetic Counseling. Practice-based competencies for genetic counselors [Internet]. Accreditation Council for Genetic Counseling; 2023 [cited 2026 Jan 1]. Available from: https://www.gceducation.org/wp-content/uploads/2024/08/ACGC_PracticeBasedCompetencies_2023.pdf
- 9. Ormond KE, Laurino MY, Barlow-Stewart K, Wessels TM, Macaulay S, Austin J, Middleton A. Genetic counseling globally: where are we now? Am J Med Genet C Semin Med Genet 2018;178:98-107. https://doi.org/10.1002/ajmg.c.31607
- 10. Hehmeyer KN, Zierhut H, Dedrick R, Dean M, Schwarting K, Bellia KS, Cragun D. The development and preliminary evaluation of the Genetic Counseling Skills Checklist. J Genet Couns 2024;33:578-591. https://doi.org/10.1002/jgc4.1758
- 11. Tak S, Lee BH, Choi IH. Development and verification of the Korean version of the Genetic Counseling Self-Efficacy Scale. J Genet Couns 2025;34:e1933. https://doi.org/10.1002/jgc4.1933
- 12. Scouten RW, Wesson M, Wetherill L, Vance GH, Delk PR. Genetic counseling program remediation practices for students underperforming in clinical skills: an exploratory study. J Genet Couns 2024;33:4-14. https://doi.org/10.1002/jgc4.1710
- 13. Berg J, Hoskovec J, Hashmi SS, McCarthy Veach P, Ownby A, Singletary CN. Relieving the bottleneck: an investigation of barriers to expansion of supervision networks at genetic counseling training programs. J Genet Couns 2018;27:241-251. https://doi.org/10.1007/s10897-017-0142-3
- 14. Pan V, Yashar BM, Pothast R, Wicklund C. Expanding the genetic counseling workforce: program directors’ views on increasing the size of genetic counseling graduate programs. Genet Med 2016;18:842-849. https://doi.org/10.1038/gim.2015.179
- 15. Cho MT, Davis C, Lowe C, Flynn M, Jamal L, Bajaj K, Atzinger C, Erby LH. Beyond multiple choice: clinical simulation as a rigorous and inclusive method for assessing genetic counseling competencies. J Genet Couns 2024;33:118-123. https://doi.org/10.1002/jgc4.1878
- 16. Kessler LJ, LaMarra D, MacFarlane IM, Heller M, Valverde KD. Characterizing standardized patients and genetic counseling graduate education. J Genet Couns 2021;30:493-502. https://doi.org/10.1002/jgc4.1335
- 17. Elendu C, Amaechi DC, Okatta AU, Amaechi EC, Elendu TC, Ezeh CP, Elendu ID. The impact of simulation-based training in medical education: a review. Medicine (Baltimore) 2024;103:e38813. https://doi.org/10.1097/MD.0000000000038813
- 18. Xu XF, Wang Y, Wang YY, Song M, Xiao WG, Bai Y. Role-playing is an effective instructional strategy for genetic counseling training: an investigation and comparative study. BMC Med Educ 2016;16:235. https://doi.org/10.1186/s12909-016-0756-4
- 19. Choi IH, Koo YM. Accreditation for genetic counselors and a master’s program in genetic counseling and its ethics education. J Korean Bioethics Assoc 2020;21(1):41-56. https://doi.org/10.37305/JKBA.2020.06.21.1.41
- 20. Bharti RK. Contribution of medical education through role playing in community health promotion: a review. Iran J Public Health 2023;52:1121-1128. https://doi.org/10.18502/ijph.v52i6.12954
- 21. Blaine SM, Carroll JC, Rideout AL, Glendon G, Meschino W, Shuman C, Telner D, Van Iderstine N, Permaul J. Interactive genetic counseling role-play: a novel educational strategy for family physicians. J Genet Couns 2008;17:189-195. https://doi.org/10.1007/s10897-007-9142-z
- 22. Dunlop KL, Barlow-Stewart K, Butow P, Heinrich P. A model of professional development for practicing genetic counselors: adaptation of communication skills training in oncology. J Genet Couns 2011;20:217-230. https://doi.org/10.1007/s10897-010-9340-y
- 23. Kneebone R. Evaluating clinical simulations for learning procedural skills: a theory-based approach. Acad Med 2005;80:549-553. https://doi.org/10.1097/00001888-200506000-00006
- 24. McIlvried DE, Prucka SK, Herbst M, Barger C, Robin NH. The use of role-play to enhance medical student understanding of genetic counseling. Genet Med 2008;10:739-744. https://doi.org/10.1097/GIM.0b013e318187762e
- 25. Nestel D, Tierney T. Role-play for medical students learning about communication: guidelines for maximising benefits. BMC Med Educ 2007;7:3. https://doi.org/10.1186/1472-6920-7-3
- 26. Andoni L, Hobson WL, Carey JC, Dent KM. Training methods for delivering difficult news in genetic counseling and genetics residency training programs. J Genet Couns 2018;27:1497-1505. https://doi.org/10.1007/s10897-018-0271-3
- 27. Huang LJ, Huang HC, Chuang CL, Chang SL, Tsai HC, Lu DY, Yang YY, Chang CC, Hsu HC, Lee FY. Role-play of real patients improves the clinical performance of medical students. J Chin Med Assoc 2021;84:183-190. https://doi.org/10.1097/JCMA.0000000000000431
- 28. Rudinsky SL, Weissbrod E, Cole R. The impact of the patient role on medical student learning during peer simulation: a qualitative phenomenological study. Simul Healthc 2024;19:11-20. https://doi.org/10.1097/SIH.0000000000000698
- 29. Ben Abdelaziz R, Boudabous H, Hajji H, Ben Messaoud S, Azzouz H, Ben Chehida A, Tebib N. Role play for genetic counseling learning: value and students perceptions. Tunis Med 2019;97:426-431.
- 30. Cheng A, Grant V, Huffman J, Burgess G, Szyld D, Robinson T, Eppich W. Coaching the debriefer: peer coaching to improve debriefing quality in simulation programs. Simul Healthc 2017;12:319-325. https://doi.org/10.1097/SIH.0000000000000232
- 31. Fanning RM, Gaba DM. The role of debriefing in simulation-based learning. Simul Healthc 2007;2:115-125. https://doi.org/10.1097/SIH.0b013e3180315539
- 32. Sawyer T, Eppich W, Brett-Fleegler M, Grant V, Cheng A. More than one way to debrief: a critical review of healthcare simulation debriefing methods. Simul Healthc 2016;11:209-217. https://doi.org/10.1097/SIH.0000000000000148
- 33. Shinnick MA, Woo M, Horwich TB, Steadman R. Debriefing: the most important component in simulation? Clin Simul Nurs 2011;7:e105-e111. https://doi.org/10.1016/j.ecns.2010.11.005
- 34. Kim YJ, Yoo JH. The utilization of debriefing for simulation in healthcare: a literature review. Nurse Educ Pract 2020;43:102698. https://doi.org/10.1016/j.nepr.2020.102698