Abstract
-
Purpose
Neck pain is a leading musculoskeletal cause of disability in the United States. This study aimed to assess temporal, geographic, and demographic disparities in its burden across US states from 1990 to 2021.
-
Methods
Global Burden of Disease 2021 data for all 50 US states and the District of Columbia were analyzed for 1990–2021. Counts and age-standardized rates per 100,000 population for prevalence, incidence, and years lived with disability (YLD) were compared by region, state, sex, age group, and sociodemographic index (SDI) level.
-
Results
In 2021, neck pain accounted for 9,430,000 (95% uncertainty interval [UI], 7,400,000–11,590,000) prevalent cases, 1,900,000 (95% UI, 1,490,000–2,320,000) incident cases, and 920,000 (95% UI, 620,000–1,300,000) YLD, increases of 41.17%, 37.44%, and 38.72%, respectively, from 1990. Although age-standardized incidence increased globally by 1.18% (0.07%–2.39%) over 1990–2021, the United States had small declines in age-standardized incidence (−0.11%; 95% UI, −0.18% to −0.06%), prevalence (−0.20%; 95% UI, −0.32% to −0.10%), and YLD (−1.12%; 95% UI, −2.02% to −0.22%). Neck pain rates were highest in the District of Columbia, Georgia, and Delaware and lowest in North Carolina, Alaska, and Wyoming. The burden peaked at ages 40–49 years and was higher in females. Age-standardized YLD rates for neck pain were significantly positively correlated with the SDI (Spearman’s ρ=0.601, P<0.001).
-
Conclusion
The geographic and demographic disparities in neck pain burden across US states indicate a need for targeted interventions.
-
Keywords: Neck pain; Epidemiology; Global Burden of Disease; United States
Introduction
Neck pain is clinically defined as pain in the posterior cervical region, extending from the nuchal line superiorly to the first thoracic spinous process inferiorly, with or without radiation to the upper extremities [
1]. It is widely associated with restricted cervical mobility and impaired daily functioning [
2]. Neck pain is a major musculoskeletal condition worldwide, including in the United States [
3], with recent estimates placing global age-standardized prevalence among adults at approximately 2.7% [
4]. Its chronic, recurrent course imposes substantial personal, societal, and economic burdens. In the United States, low back and neck pain accounted for the highest spending among 154 health conditions studied, reaching an estimated $134.5 billion in 2016 [
5]. Common musculoskeletal pain conditions have also been estimated to cost US employers approximately $61.2 billion annually in lost productive time [
6]. Musculoskeletal conditions, including neck pain, are among the leading contributors to disability, accounting for a substantial burden measured in years lived with disability (YLD) [
3,
7].
The Global Burden of Disease (GBD) Study 2021, conducted by the Institute for Health Metrics and Evaluation (IHME) at the University of Washington, is among the most comprehensive efforts to quantify health loss systematically worldwide. It covers 371 diseases and injuries across 204 countries and territories from 1990 to the present [
8,
9]. Neck pain burden varies considerably across US states, potentially reflecting differences in demographic composition, socioeconomic factors, healthcare access, and occupational exposure [
9,
10]. This variation is particularly relevant in the context of population aging and interstate disparities in healthcare access [
8,
11,
12]. Although global and national studies have characterized neck pain trends [
2,
4,
13], existing US-focused analyses remain limited: national survey data on general pain cover only 2002–2018 [
12], and state-level neck pain assessments have used a single year of Google search-volume data as a behavioral proxy rather than direct epidemiological burden estimates [
14]. Similarly, US-focused resources such as the Burden of Musculoskeletal Diseases in the US report rely primarily on healthcare utilization data—clinic visits and hospital discharges—reported as periodic, multiyear snapshots rather than continuously modeled, comparable state-level epidemiological estimates spanning 3 decades [
3]. This study therefore aimed to evaluate neck pain burden systematically across all US states from 1990 to 2021 using validated metrics from the GBD Study 2021.
Methods
Data source and study population
Neck pain burden was analyzed using the GBD 2021 dataset in accordance with the Guidelines for Accurate and Transparent Health Estimates Reporting [
15]. Because the GBD Study uses de-identified data, informed consent was not required. This study was approved by the Institutional Review Board (IRB) of Ewha Womans University Seoul Hospital (IRB no. SEUMC 2023-10-040).
Neck pain data were obtained from the GBD 2021 database, which contained epidemiological estimates for 371 diseases and injuries across 21 GBD regions and 204 countries and territories for 1990–2021. The data were accessed through the Global Health Data Exchange (
https://ghdx.healthdata.org). Estimates for all 50 US states and the District of Columbia were included in the analysis.
Neck pain was defined as cervical pain lasting at least 1 day, with or without radiation to the upper extremities [
1]. The neck was defined as the posterior region extending from the nuchal line superiorly to the first thoracic spinous process inferiorly. Neck pain codes in the International Classification of Diseases, 10th Revision, covered cervicalgia (M54.2), cervical disc disorders (M50), and cervicocranial and cervicobrachial syndromes (M53.0–M53.1). Other disorders of the cervical region were coded as 723 in the International Classification of Diseases, Ninth Revision.
GBD estimates were generated from multiple population-based data sources using the standardized IHME modeling framework. Additional US data came from the Medical Expenditure Panel Survey (MEPS), Medicare administrative claims, and state health department records. Systematic bias in nonreference US data sources was adjusted using crosswalks estimated by meta-regression—Bayesian, regularized, trimmed [
8].
Introduced by the IHME in 2015, the sociodemographic index (SDI) is a composite measure of developmental status across countries and regions. It is derived from average income, educational attainment, and fertility rates and incorporates the association between social progress and population health outcomes [
16]. Although all US states were in the high-SDI quintile (>0.81), meaningful variation remained within this narrow range. The analysis therefore examined whether these within-band differences were associated with neck pain burden, without assuming that the findings would generalize to lower-SDI settings outside the United States [
10].
GBD estimates were modeled using DisMod-MR ver. 2.1 (Institute for Health Metrics and Evaluation, University of Washington), a Bayesian meta-regression framework that uses a compartmental disease model based on differential equations to enforce internal consistency among prevalence, incidence, and remission. This ensures that estimates of each epidemiological parameter are mathematically coherent with the others [
9,
10]. All estimates are reported with 95% uncertainty intervals (UIs) derived from 500 data draws, with the 97.5th and 2.5th percentiles defining the upper and lower bounds, respectively [
10]. Counts for the 4 US Census Bureau regions and 9 divisions were calculated by summing the counts of their constituent states, so that regional and divisional totals add up to the national total; because GBD does not publish region- or division-level estimates, the uncertainty bounds of these summed counts were obtained by summing state-level bounds and should be regarded as approximate.
Spearman’s rank correlation was used to examine whether state-level variation in neck pain burden was associated with sociodemographic development, as measured by the SDI. Choropleth maps of burden were used to visualize spatial clustering and interstate disparities. Temporal trends in age-standardized rates over 1990–2021 were described by visually inspecting annual estimates. Given the descriptive, hypothesis-generating nature of these state-level comparisons, uncorrected P-values are reported throughout, as discussed further in the limitations section.
Results
Neck pain burden trajectory across US states: 1990–2021
Neck pain ranked 16th among the leading causes of disability in the United States in 1990, 18th in 2010, and 14th in 2021. Its ranking thus rose overall during the study period, and it remained among the leading musculoskeletal contributors to disability [
8].
In 2021, prevalent cases totaled 9.43 million (95% UI, 7.40–11.59 million), an increase of 41.17% (95% UI, 33.95%–48.92%) from 1990. In contrast, the age-standardized prevalence rate decreased marginally to 2,397.27 per 100,000 (95% UI, 1,850.62–3,002.28 per 100,000), a change of −0.20% (95% UI, −0.32% to −0.10%) (
Supplement 1).
Incident cases likewise totaled 1.90 million (95% UI, 1.49–2.32 million) in 2021, an increase of 37.44% (95% UI, 30.12%–45.41%) from 1990. The age-standardized incidence rate, however, declined slightly to 506.12 per 100,000 (95% UI, 397.88–614.23 per 100,000), a change of −0.11% (95% UI, −0.18% to −0.06%) (
Supplement 2).
Absolute YLD estimates increased from 0.66 million in 1990 to 0.92 million (95% UI, 0.62–1.30 million) in 2021, an increase of 38.72% (95% UI, 31.55%–46.36%). In contrast, the age-standardized YLD rate decreased by 1.12% (95% UI, −2.02% to −0.22%) to 236.52 per 100,000 (95% UI, 157.55–342.46 per 100,000) in 2021 (
Supplements 3–
5).
Neck pain burden varied among the major US geographic regions over 1990–2021. The Northeast, Midwest, and South had small reductions in age-standardized prevalence and incidence rates, but no significant changes in YLD rates. In the West, none of the 3 rates changed significantly (
Table 1,
Supplement 6).
Among divisions, East South Central had the highest age-standardized prevalence rate in 2021, at 2,409.01 per 100,000 (95% UI, 1,862.14–3,014.77), whereas South Atlantic had the lowest, at 2,363.83 per 100,000 (95% UI, 1,815.53–2,970.66). The same divisions had the highest and lowest age-standardized incidence rates: 507.95 per 100,000 (95% UI, 399.26–615.80) in East South Central and 500.77 per 100,000 (95% UI, 392.13–610.55) in South Atlantic. The age-standardized YLD rate was highest in New England, at 238.03 per 100,000 (95% UI, 158.38–342.23), and lowest in South Atlantic, at 233.00 per 100,000 (95% UI, 153.18–337.40) (
Table 1).
From 1990 to 2021, West South Central had the largest relative reductions in age-standardized prevalence (−0.28%; 95% UI, −0.40% to −0.15%) and incidence rates (−0.16%; 95% UI, −0.25% to −0.09%). Age-standardized YLD measures, however, showed no statistically significant changes (
Table 1).
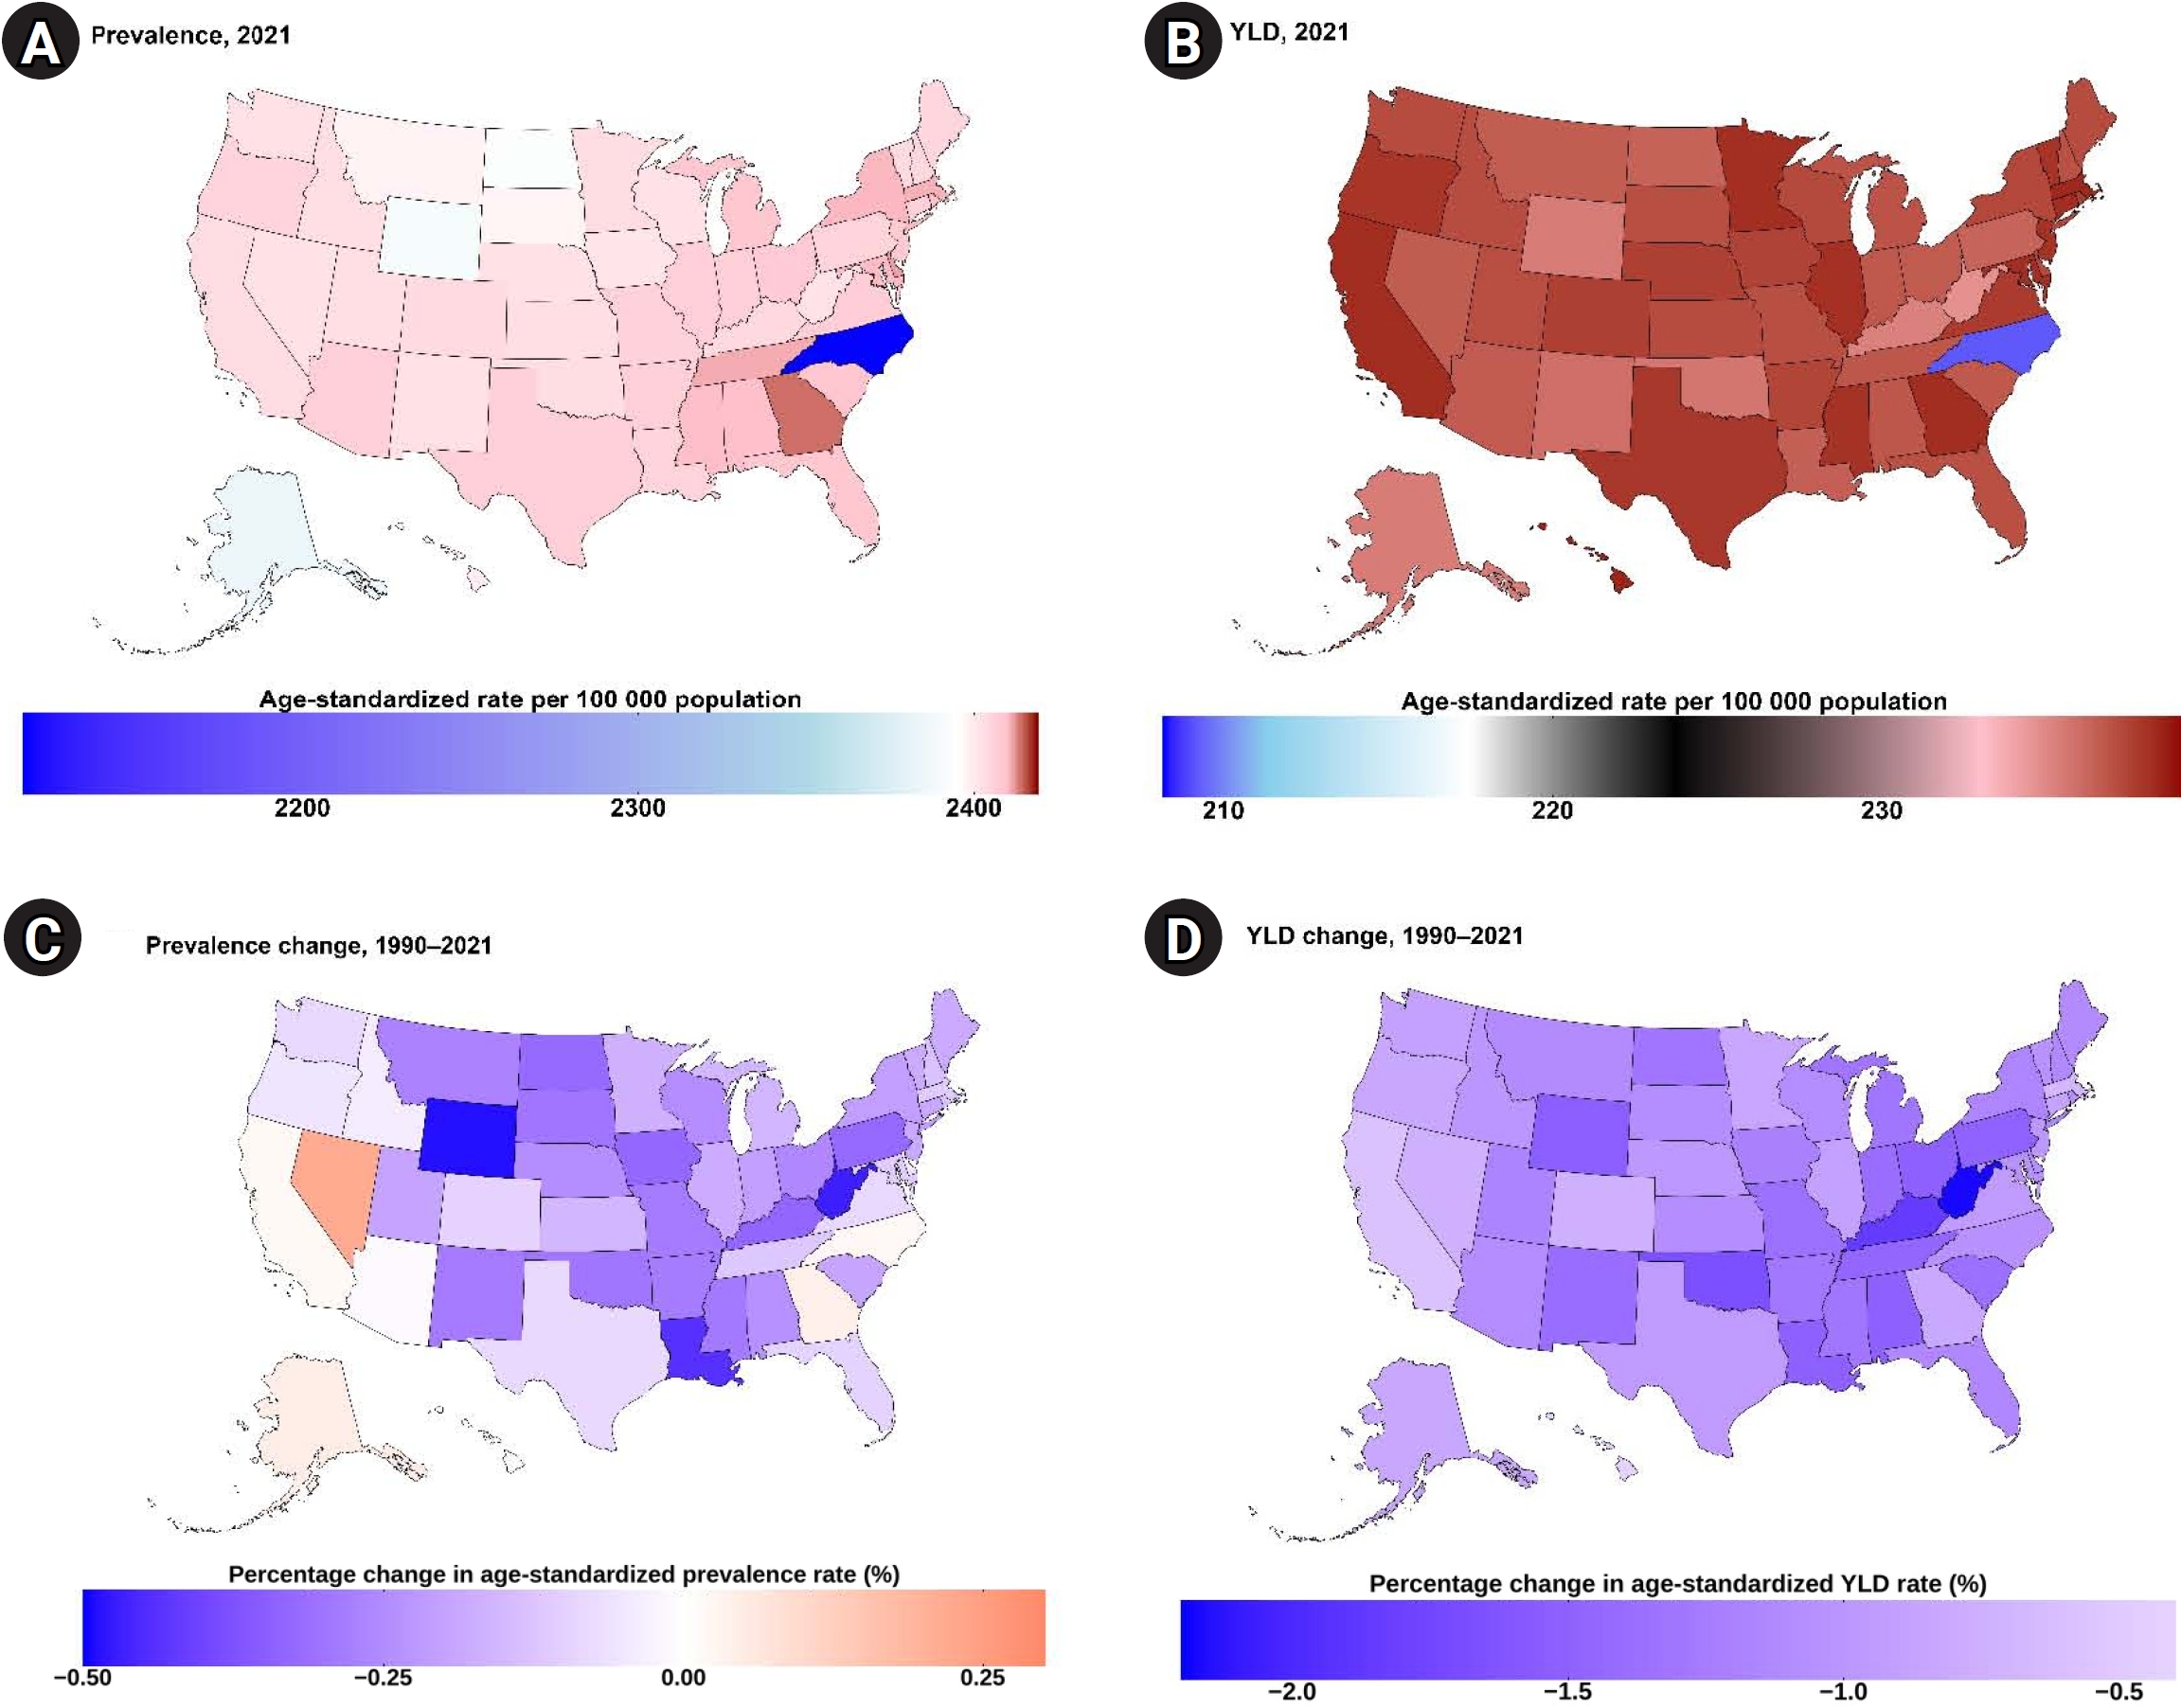
Neck pain burden varied considerably across US states in 2021. Age-standardized prevalence rates per 100,000 were highest in the District of Columbia (2,418.69; 95% UI, 1,872.06–3,028.00), Georgia (2,414.23; 95% UI, 1,866.65–3,022.25), and Delaware (2,411.57; 95% UI, 1,863.91–3,019.02). North Carolina had the lowest rate (2,117.28; 95% UI, 1,562.06–2,727.70) (
Table 1,
Fig. 1,
Supplements 7,
8).
Age-standardized incidence rates followed a similar geographic pattern. Rates per 100,000 were highest in the District of Columbia (509.91; 95% UI, 400.68–618.27), Georgia (508.73; 95% UI, 399.78–616.77), and Delaware (508.22; 95% UI, 399.47–616.16), and lowest in North Carolina (462.03; 95% UI, 353.71–582.12) (
Table 1,
Fig. 1,
Supplements 9,
10).
Age-standardized YLD rates per 100,000 indicated the highest disability burden in the District of Columbia (239.24; 95% UI, 158.86–344.07), Georgia (238.18; 95% UI, 157.67–341.69), and Delaware (237.28; 95% UI, 156.90–341.21). North Carolina had the lowest YLD rate (209.18; 95% UI, 135.10–316.54) (
Table 1,
Fig. 1,
Supplements 10,
11).
State-level trends differed over 1990–2021. The largest significant reductions in age-standardized prevalence rates occurred in Wyoming (−0.49%; 95% UI, −0.68 to −0.31), West Virginia (−0.47%; 95% UI, −0.66 to −0.29), and Louisiana (−0.44%; 95% UI, −0.61 to −0.27). Age-standardized incidence rates also declined in these states, by −0.34%, −0.29%, and −0.28%, respectively. Conversely, Nevada had significant increases in both prevalence and incidence rates (+0.22%; 95% UI, 0.13–0.32) (
Table 1,
Fig. 1).
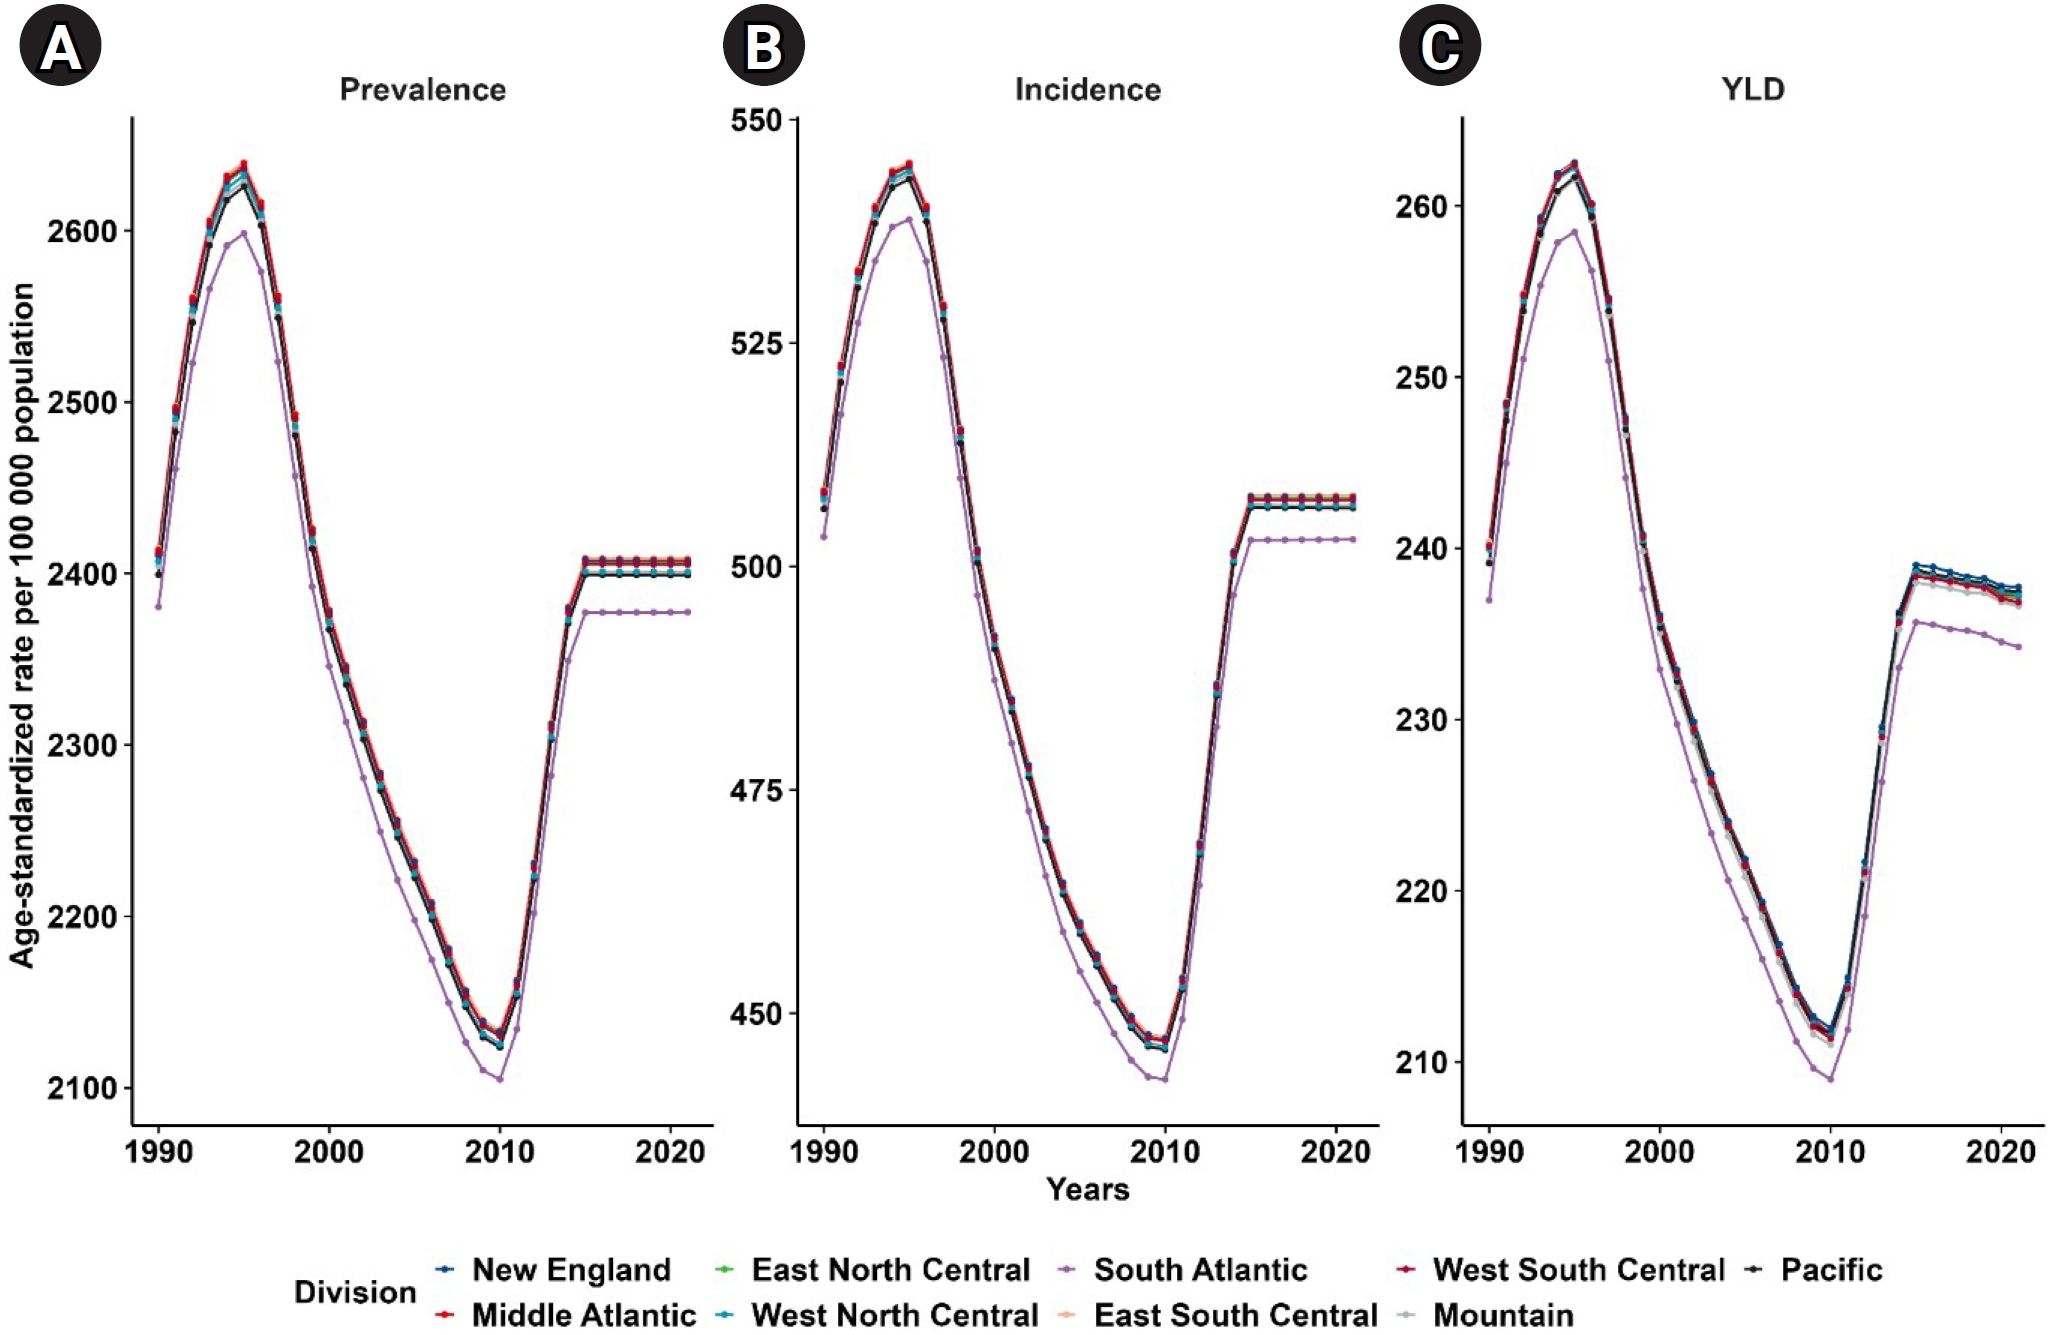
Visual inspection of the 1990–2021 trends showed a consistent U-shaped pattern in age-standardized prevalence, incidence, and YLD rates for neck pain across US divisions (
Fig. 2).
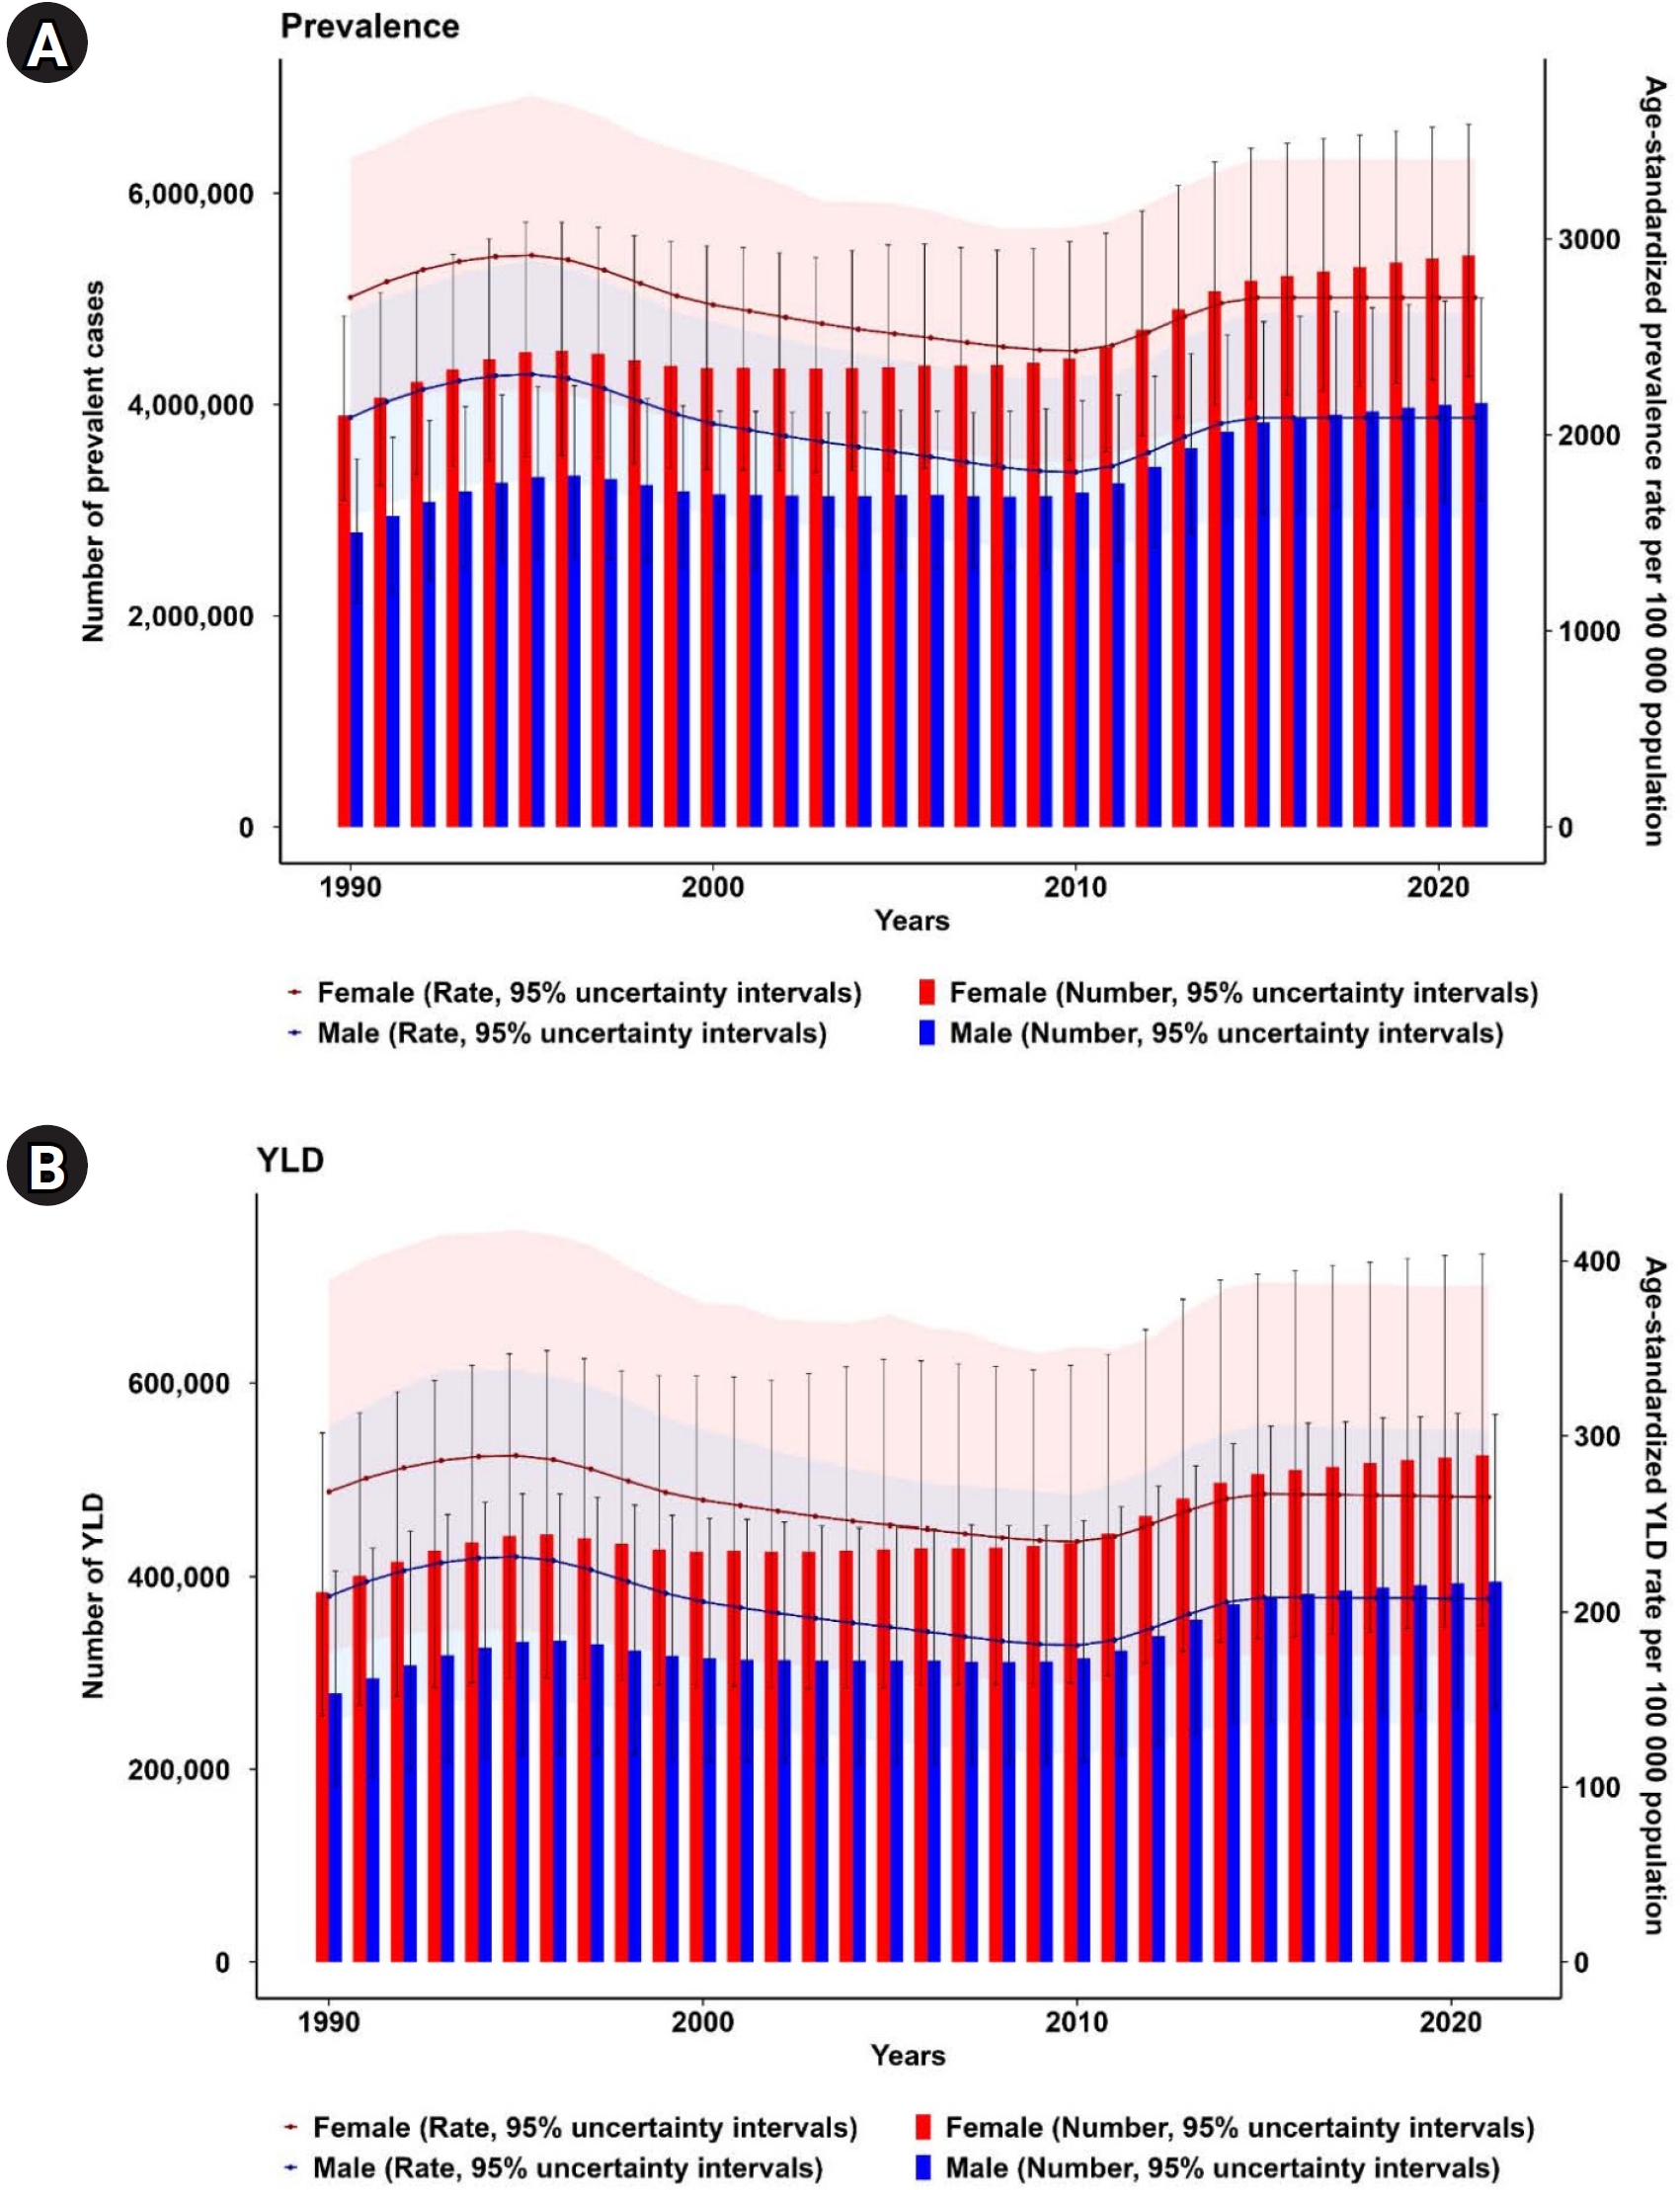
In 2021, all neck pain metrics were higher in females than in males. Age-standardized prevalence was 2,700.48 per 100,000 (95% UI, 2,105.34–3,407.78) in females and 2,087.73 per 100,000 (95% UI, 1,578.93–2,621.24) in males. From 1990 to 2021, age-standardized prevalence rates declined slightly in both sexes despite increases in absolute case counts (
Supplement 1).
Incidence rates showed a similar pattern by sex. In 2021, age-standardized incidence was 555.04 per 100,000 (95% UI, 428.13–679.07) in females and 456.92 per 100,000 (95% UI, 360.91–553.57) in males. Both sexes had equivalent small declines in incidence rates over 1990–2021, despite increases in the absolute numbers of incident cases (
Supplement 2).
Disability burden was also higher in females: the age-standardized YLD rate in 2021 was 265.07 per 100,000 (95% UI, 175.19–386.22), compared with 207.41 per 100,000 (95% UI, 136.37–303.02) in males. Neither sex had a statistically significant change in age-standardized YLD rates from 1990 to 2021, although absolute YLD increased (
Supplements 3,
12).
Fig. 3 illustrates these trends.
Peak ages differed by burden metric (
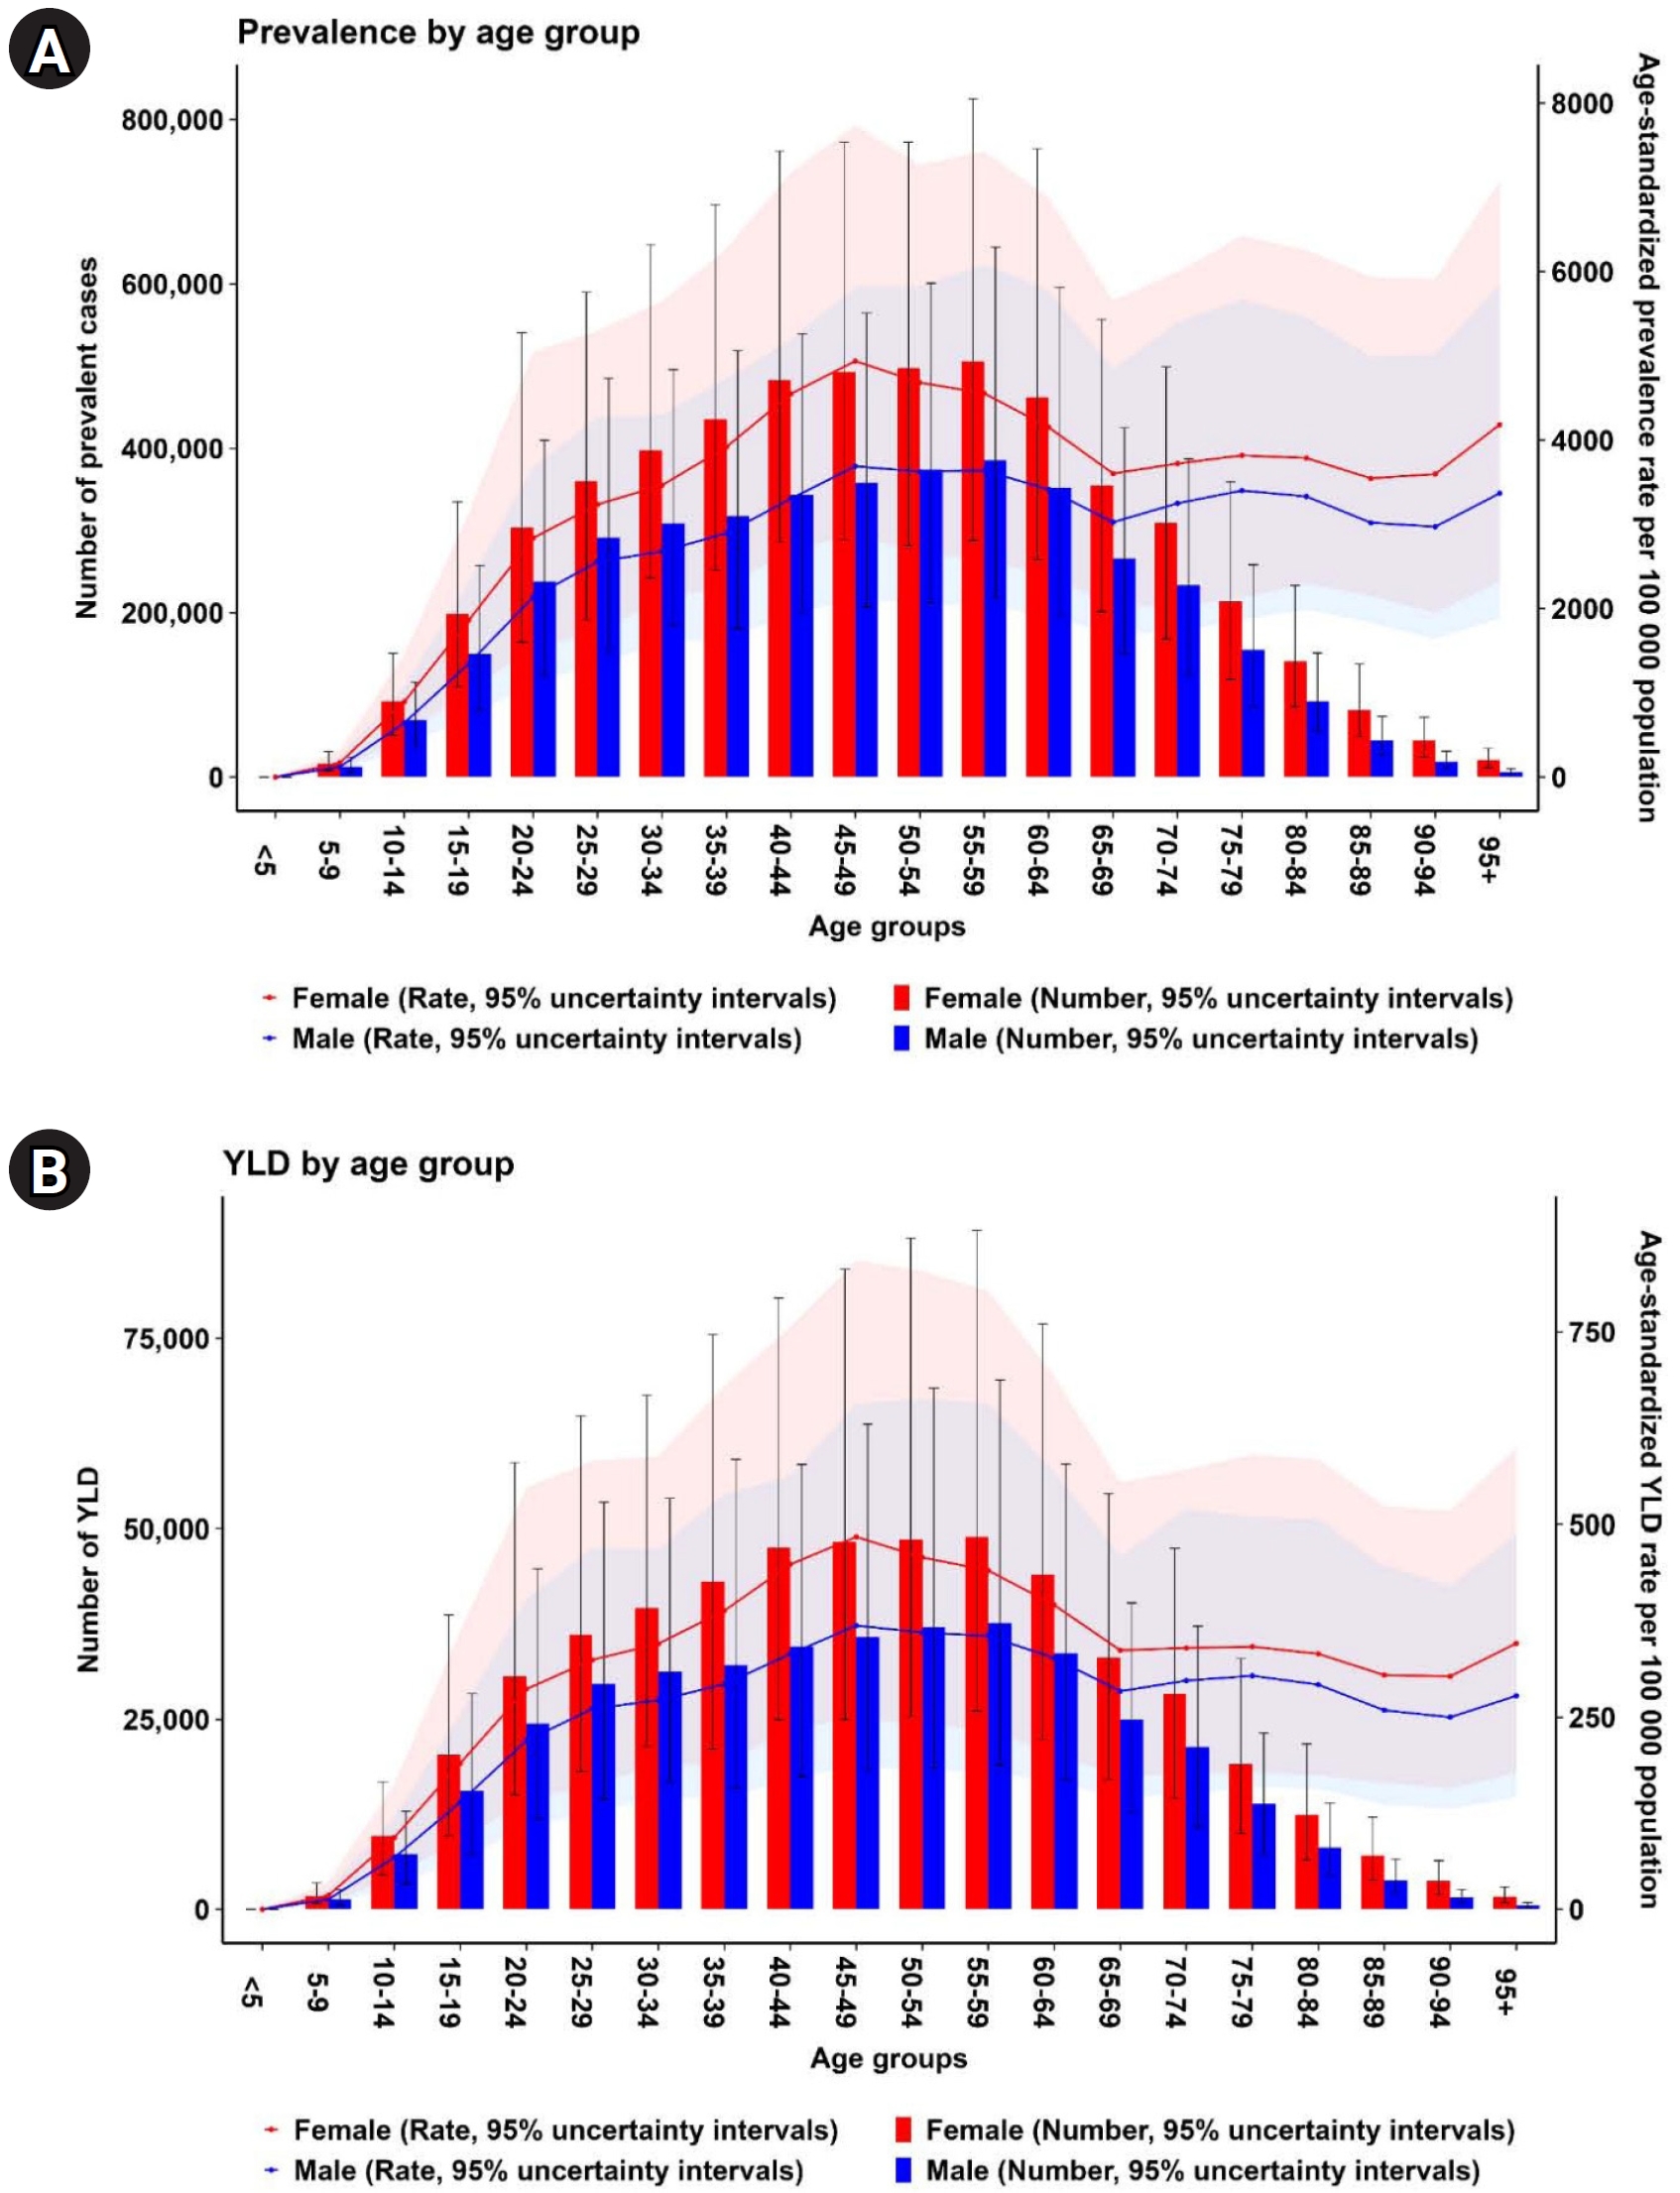
Supplement 13). In both sexes, prevalence and YLD rates were highest at ages 45–49 years, whereas incidence peaked at ages 40–44 years (
Fig. 4,
Supplement 14).
Supplement 15 presents the associations between SDI and neck pain burden across US states in 2021. SDI was significantly positively associated with age-standardized YLD rates (Spearman’s ρ=0.60, P<0.001). In contrast, its correlations with age-standardized prevalence (ρ=0.15, P=0.29) and incidence rates (ρ=0.15, P=0.30) were weak and not statistically significant. Nevertheless, the 4 East South Central states (Alabama, Kentucky, Mississippi, and Tennessee) and Georgia had a higher neck pain burden despite relatively lower SDI scores than other regions.
Discussion
Age-standardized prevalence and incidence rates for neck pain remained relatively stable over the 3-decade study period, whereas absolute case counts increased substantially, reflecting demographic shifts in the US population. The Midwest had the greatest reductions in both rates. Sex disparities persisted throughout the study period, with females consistently having higher rates than males across all metrics. Burden was highest in middle-aged individuals. Sociodemographic development was positively associated with neck pain burden, although regional differences were also evident.
The slight decline in age-standardized neck pain prevalence in the United States, alongside the substantial increase in absolute cases over 1990–2021, could reflect the combined effects of demographic shifts [
17,
18], healthcare access patterns [
19,
20], and changing risk factor profiles [
4,
21] in the United States. These trends contrast with global patterns over the same period [
2,
13,
22], suggesting distinct epidemiological dynamics in the United States.
The U-shaped temporal pattern, with rates falling to a nadir around 2010 before rising again (
Supplement 16), coincided with major changes in device use and work patterns. Smartphone ownership among US adults rose rapidly during this period, alongside increases in prolonged computer use and sedentary desk work. Given their known associations with neck pain risk, these are plausible contributors, although they were not directly tested [
23].
Geographic variation in neck pain burden across US states likely reflects multiple factors operating at different scales. Burden was higher in the East South Central states (Alabama, Kentucky, Mississippi, and Tennessee) and Georgia. These areas overlap substantially with Appalachia and the southeastern United States, where disproportionately high prevalence of musculoskeletal disorders and chronic pain has been documented. These regions have lower socioeconomic status, more physically demanding occupations, and relatively limited healthcare access [
12,
14,
19,
24]. Historically, employment has been more concentrated in mining, manufacturing, and agriculture, which involve repetitive motion, heavy lifting, and prolonged awkward postures. Previous occupational health research has associated these exposures with musculoskeletal pain, including neck pain. Although this occupational profile offers a plausible context for the elevated burden in these states, the ecological, state-level design cannot establish a direct causal relationship between specific industries and individual neck pain risk [
4,
23].
Socioeconomic disparities may further exacerbate neck pain burden. Alabama, Kentucky, Mississippi, Tennessee, and Georgia had relatively low SDI scores compared with other US regions (
Supplement 15). The lower educational attainment [
25] and economic disadvantages [
23,
26] in these regions have been reported to correlate with adverse health outcomes and a higher prevalence of chronic pain [
12]. Obesity, smoking, and sedentary behaviors are also more common in these regions and have been associated with a higher prevalence of musculoskeletal pain [
8]. Previous studies have likewise documented geographic clustering of pain conditions in the southern and Appalachian United States [
11].
Previous studies have reported higher neck pain prevalence in females, with female-to-male ratios of 1.3–1.5 [
2,
22,
27]. Biological and psychosocial factors may together explain this consistently higher burden. Smaller cervical vertebrae and distinct muscle mass distributions are anatomical differences that have been suggested to increase susceptibility to neck pain in females [
28]. Pain sensitivity and inflammatory responses have been associated with hormonal influences, particularly estrogen fluctuations [
29]. Higher rates of stress, depression, and anxiety among females may also contribute to greater pain perception and disability [
30]. The disparity may also partly reflect occupational exposure to prolonged computer use and repetitive tasks in service or healthcare work [
23].
Population aging likely contributed to the rise in absolute case counts during the study period because neck pain burden peaks in middle age. As large birth cohorts entered the 45–64-year age range associated with the highest reported burden, this demographic shift would increase absolute case counts even if age-standardized rates remained stable or declined. This pattern is consistent with our finding of rising absolute burden alongside modestly declining age-standardized rates. Previous US survey analyses found the highest neck pain prevalence at ages 45–64 years, consistent with our results [
31]. These findings indicate a need for age-specific prevention strategies and future healthcare planning.
SDI was significantly positively correlated with age-standardized YLD in this study. There are 2 possible explanations. YLD estimates use severity weights derived from MEPS [
9], which may capture disability more effectively among populations seeking healthcare in more developed states. Alternatively, greater healthcare access in higher-SDI states may lead residents to report chronic pain and disability more often, without a true difference in case counts. These ecological data cannot distinguish between the 2 explanations. The finding agrees with previous GBD-based studies and research on other musculoskeletal disorders, such as back pain [
7,
22]. The higher prevalence and YLD associated with musculoskeletal pain in high-SDI countries, including the United States, also support this pattern [
22]. Despite the overall positive global correlation, some studies have reported contrasting patterns in specific populations and regions. A global study, for example, found a negative correlation between SDI and neck pain burden in young and middle-aged adults [
32]. A study of the Middle East and North Africa reported weak negative correlations in regions with intermediate SDI levels (approximately 0.62–0.82) [
33]. In our study, the East South Central states and Georgia had a higher burden despite lower SDI scores. This agrees with US national data showing a higher burden of musculoskeletal disorders in socioeconomically disadvantaged populations [
34,
35]. Higher chronic pain prevalence in low-income southern regions, including Appalachia, suggests that the relationship between SDI and neck pain burden is not purely linear. Differences in population aging, occupational exposure, education, healthcare access, and cultural factors across US regions may explain this variability [
1,
6,
13,
22,
24,
34-
38]. Together, these findings show the complex distribution of neck pain burden across US states and support multifaceted prevention and management strategies.
Several limitations should be considered when interpreting these findings. First, the analysis used modeled GBD estimates rather than direct population measurements, introducing uncertainty into burden estimates. DisMod-MR ver. 2.1 may not fully capture local differences in disease patterns or healthcare reporting, and state-level estimates may be uncertain where primary data are limited. Second, neck pain definitions and measurements varied among the studies used in GBD modeling. Self-reported pain is subject to recall bias and differences in healthcare-seeking behavior; variation in case definitions and assessment methods may also have introduced measurement error. Third, multiple statistical comparisons across 51 jurisdictions were conducted without formal adjustment for multiple testing, potentially increasing type I error, and spatial autocorrelation was not formally assessed. Fourth, the GBD framework may omit state-specific determinants, including occupational regulations, healthcare system characteristics, and environmental factors. Finally, state-level analysis may obscure within-state variation in urban–rural or local socioeconomic conditions, while the absence of individual-level data limits clinical interpretation. State-level policy differences (e.g., insurance coverage and workers’ compensation) and the pandemic-related shift to remote work were not examined and may also have influenced the estimates.
Conclusion
Age-standardized neck pain rates in the United States declined modestly from 1990 to 2021, but absolute case counts rose substantially, largely driven by population aging into the 45–64-year age range of peak burden. Geographic disparities remained substantial: burden was highest in the District of Columbia, Georgia, and Delaware and lowest in North Carolina. These findings suggest that prioritizing middle-aged adults and the states with the highest burden may benefit prevention efforts and healthcare resource allocation.
-
Authors’ contribution
Conceptualization: YC, MSP, HKK, TJS. Data curation: YC, MSP, HKK, TJS. Formal analysis: SP, DWS, JHP, TJS. Methodology: SP, DWS, JHP, TJS. Validation: SP, DWS, JHP, TJS. Project administration: YC, MSP, HKK, TJS. Funding acquisition: TJS. Writing–original draft: SP, DWS, JHP, TJS. Writing–review & editing: SP, DWS, JHP, TJS. Final approval of the manuscript: all authors.
-
Conflict of interest
No potential conflicts of interest relevant to this article were reported.
-
Funding
None.
-
Data availability
The data supporting this study are publicly available through the Global Health Data Exchange, the IHME data catalog, at https://ghdx.healthdata.org. Estimates of neck pain prevalence, incidence, and YLD across US states for 1990–2021 can be queried and downloaded using the GBD Results Tool at https://vizhub.healthdata.org/gbd-results/
-
Acknowledgments
None.
Supplementary materials
Supplement 1. Annual number of prevalent cases, age-standardized prevalence rates, and percentage change from 1990 to 2021, by sex.
Supplement 2. Annual number of incident cases, age-standardized incidence rates, and percentage change from 1990 to 2021, by sex.
Supplement 4. Numbers, age-standardized rates, and percentage change of incidence, prevalence, and YLD from 1990 to 2021, in global and the United States.
Supplement 5. Annual trends of age-standardized rates and numbers for (A) prevalence, (B) incidence, (C) YLD from 1990 to 2021 (shaded areas represent 95% uncertainty intervals).
Supplement 6. Numbers, age-standardized rates, and percentage changes of prevalence, incidence, and YLD in the United States.
Supplement 12. Annual trends of age-standardized rates and numbers for (A) prevalence (B) incidence (C) YLD from 1990 to 2021, by sex (shaded areas represent 95% uncertainty intervals).
Supplement 15. Age-standardized rates of (A) prevalence, (B) incidence, (C) YLD according to the sociodemographic index (SDI) in 2021, with linear regression (shaded areas represent 95% uncertainty intervals).
Supplement 16. Percentage change in age-standardized rates of (A) prevalence, (B) incidence, (C) YLD, from 2000 to 2010, and from 2010 to 2021.
Fig. 1.State-level distribution and temporal changes in age-standardized prevalence and years lived with disability (YLD) rates for neck pain in the United States, 1990–2021. (A) Age-standardized prevalence rate per 100,000 in 2021; (B) age-standardized YLD rate per 100,000 in 2021; (C) percentage change in age-standardized prevalence rate, 1990–2021; and (D) percentage change in age-standardized YLD rate, 1990–2021. Panels (A) and (B) show the highest rates in the District of Columbia, Georgia, and Delaware and the lowest in North Carolina, Alaska, and Wyoming. Panel (C) shows the largest decreases in age-standardized prevalence in Wyoming, West Virginia, and Louisiana, whereas Nevada shows an increase. Panel (D) shows declines in age-standardized YLD rates across most states.
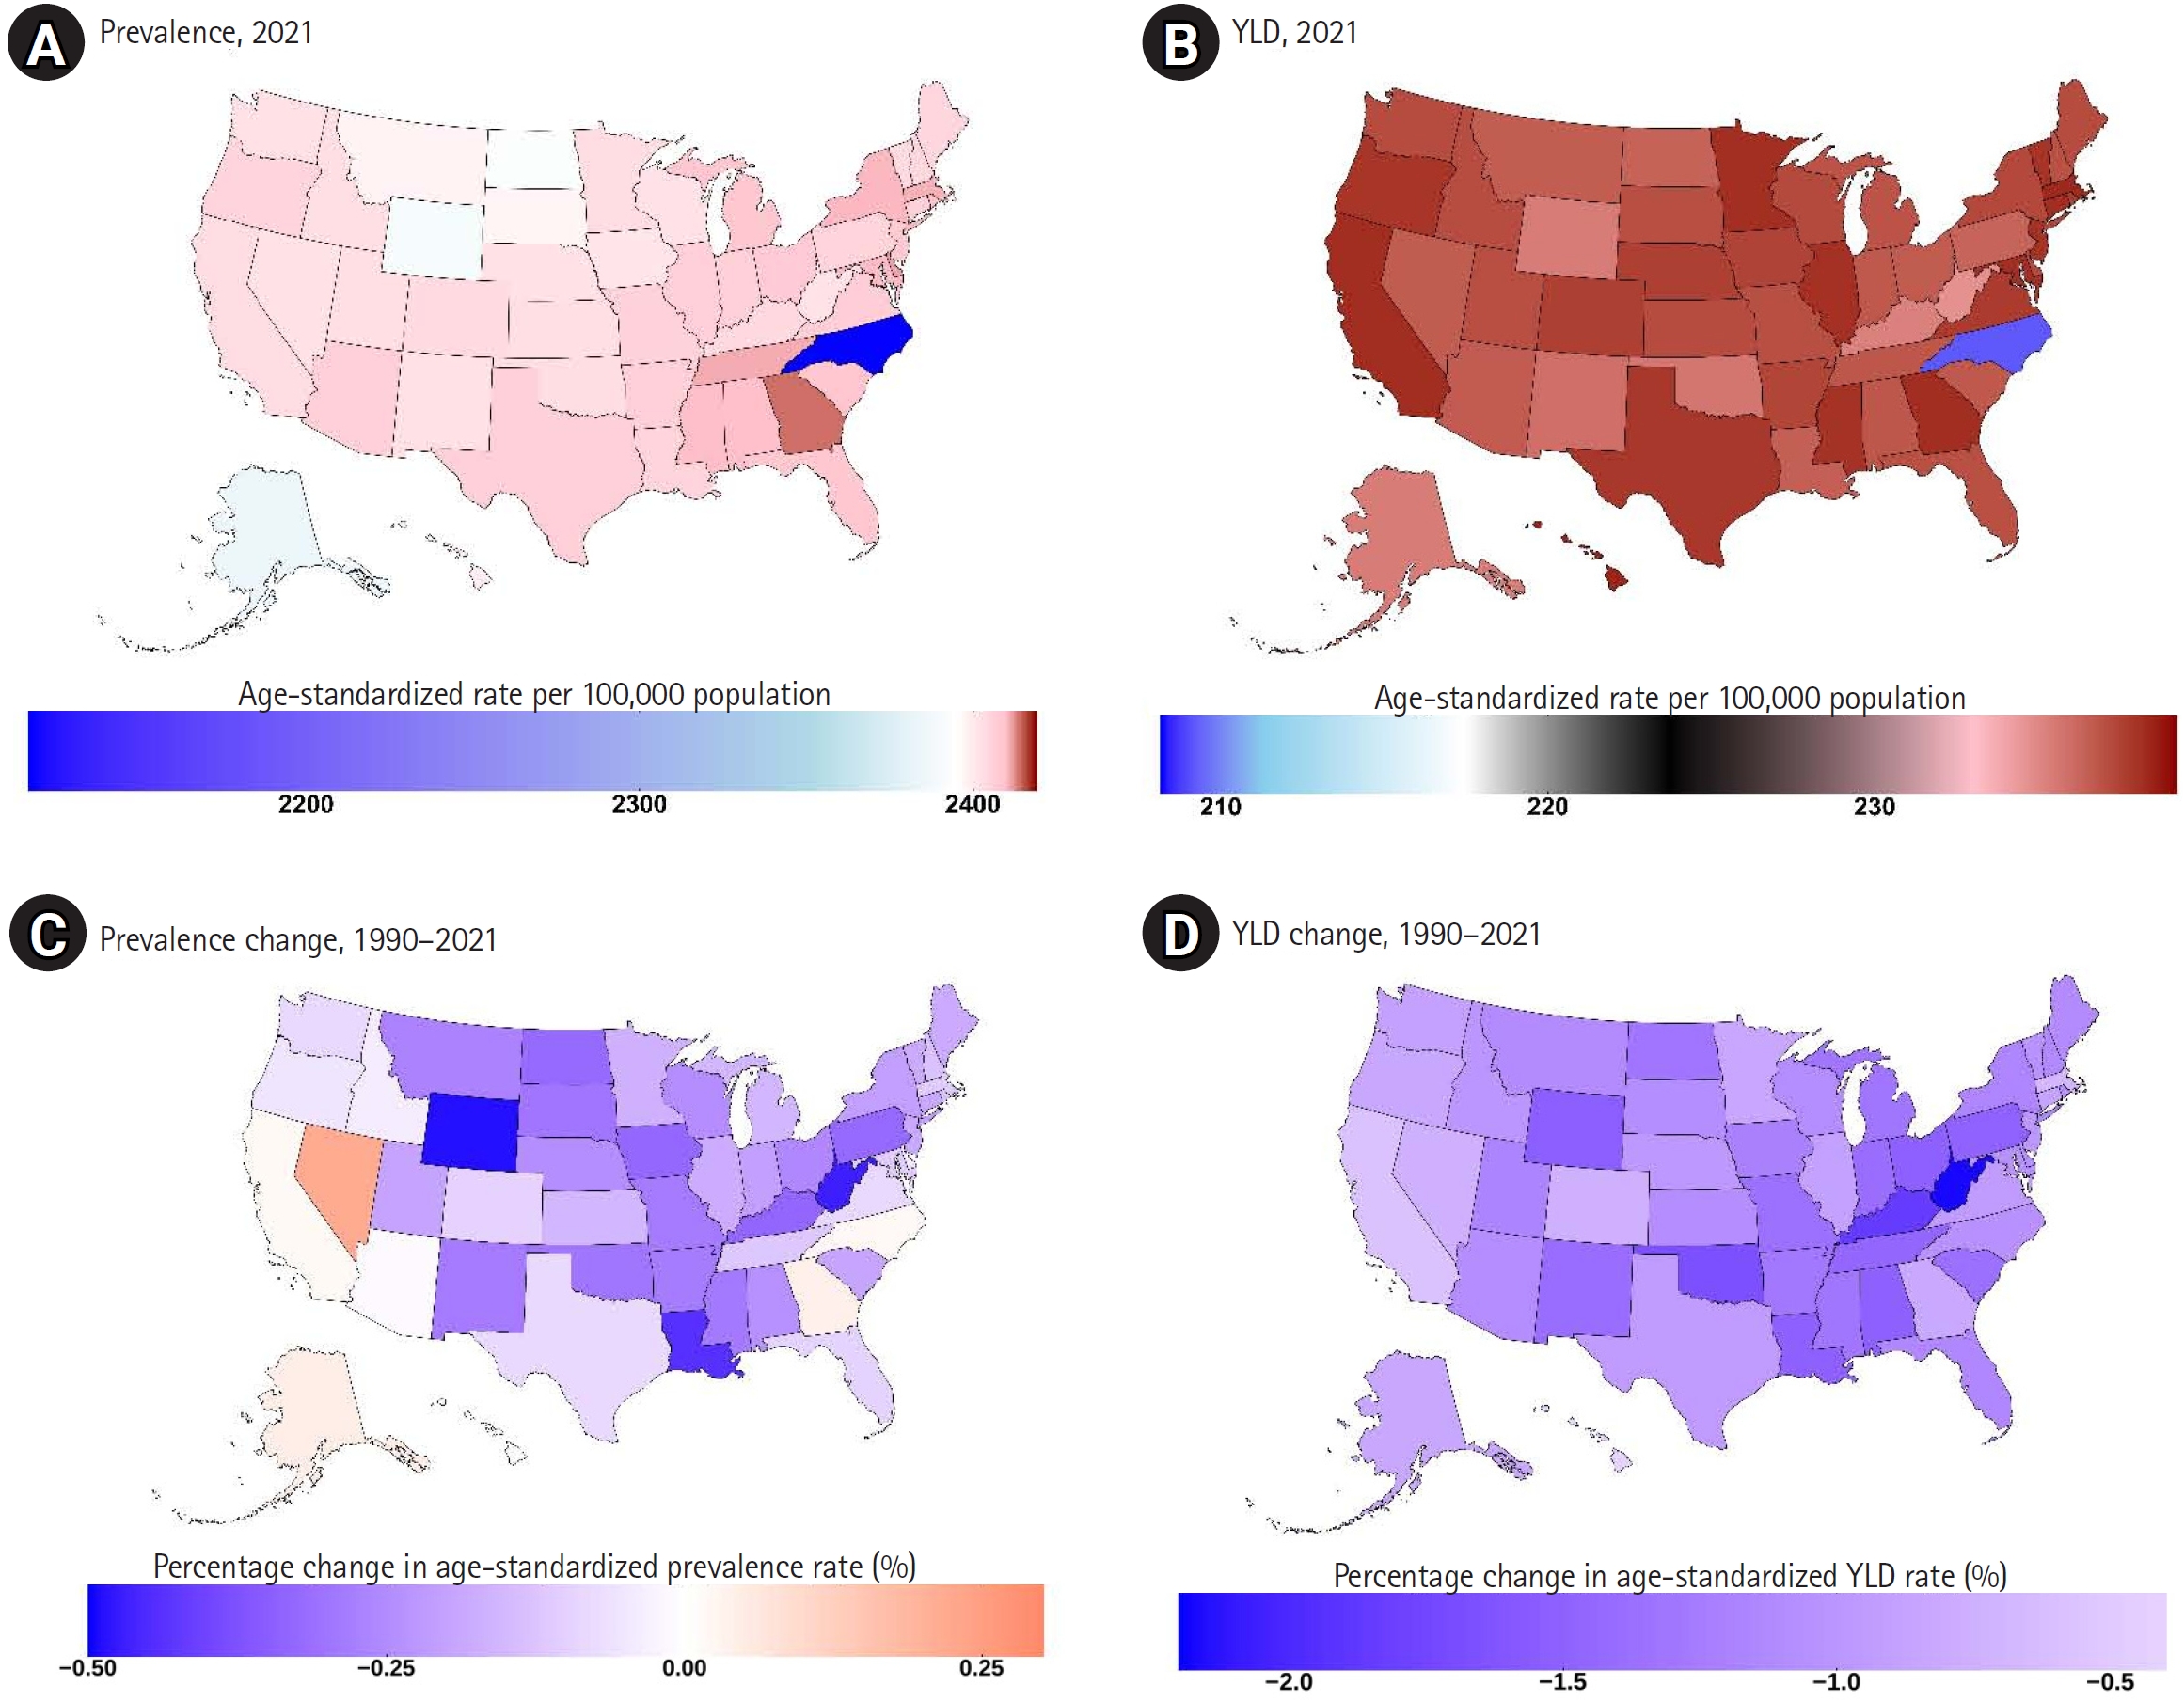
Fig. 2.(A–C) Temporal trends in age-standardized prevalence, incidence, and years lived with disability (YLD) rates for neck pain across United States divisions, 1990–2021. In all divisions, the 3 rates initially increased from 1990 to the early 2000s, then declined to their lowest levels around 2010 before increasing slightly or stabilizing. South Atlantic consistently had the lowest rates for all 3 metrics throughout the study period.
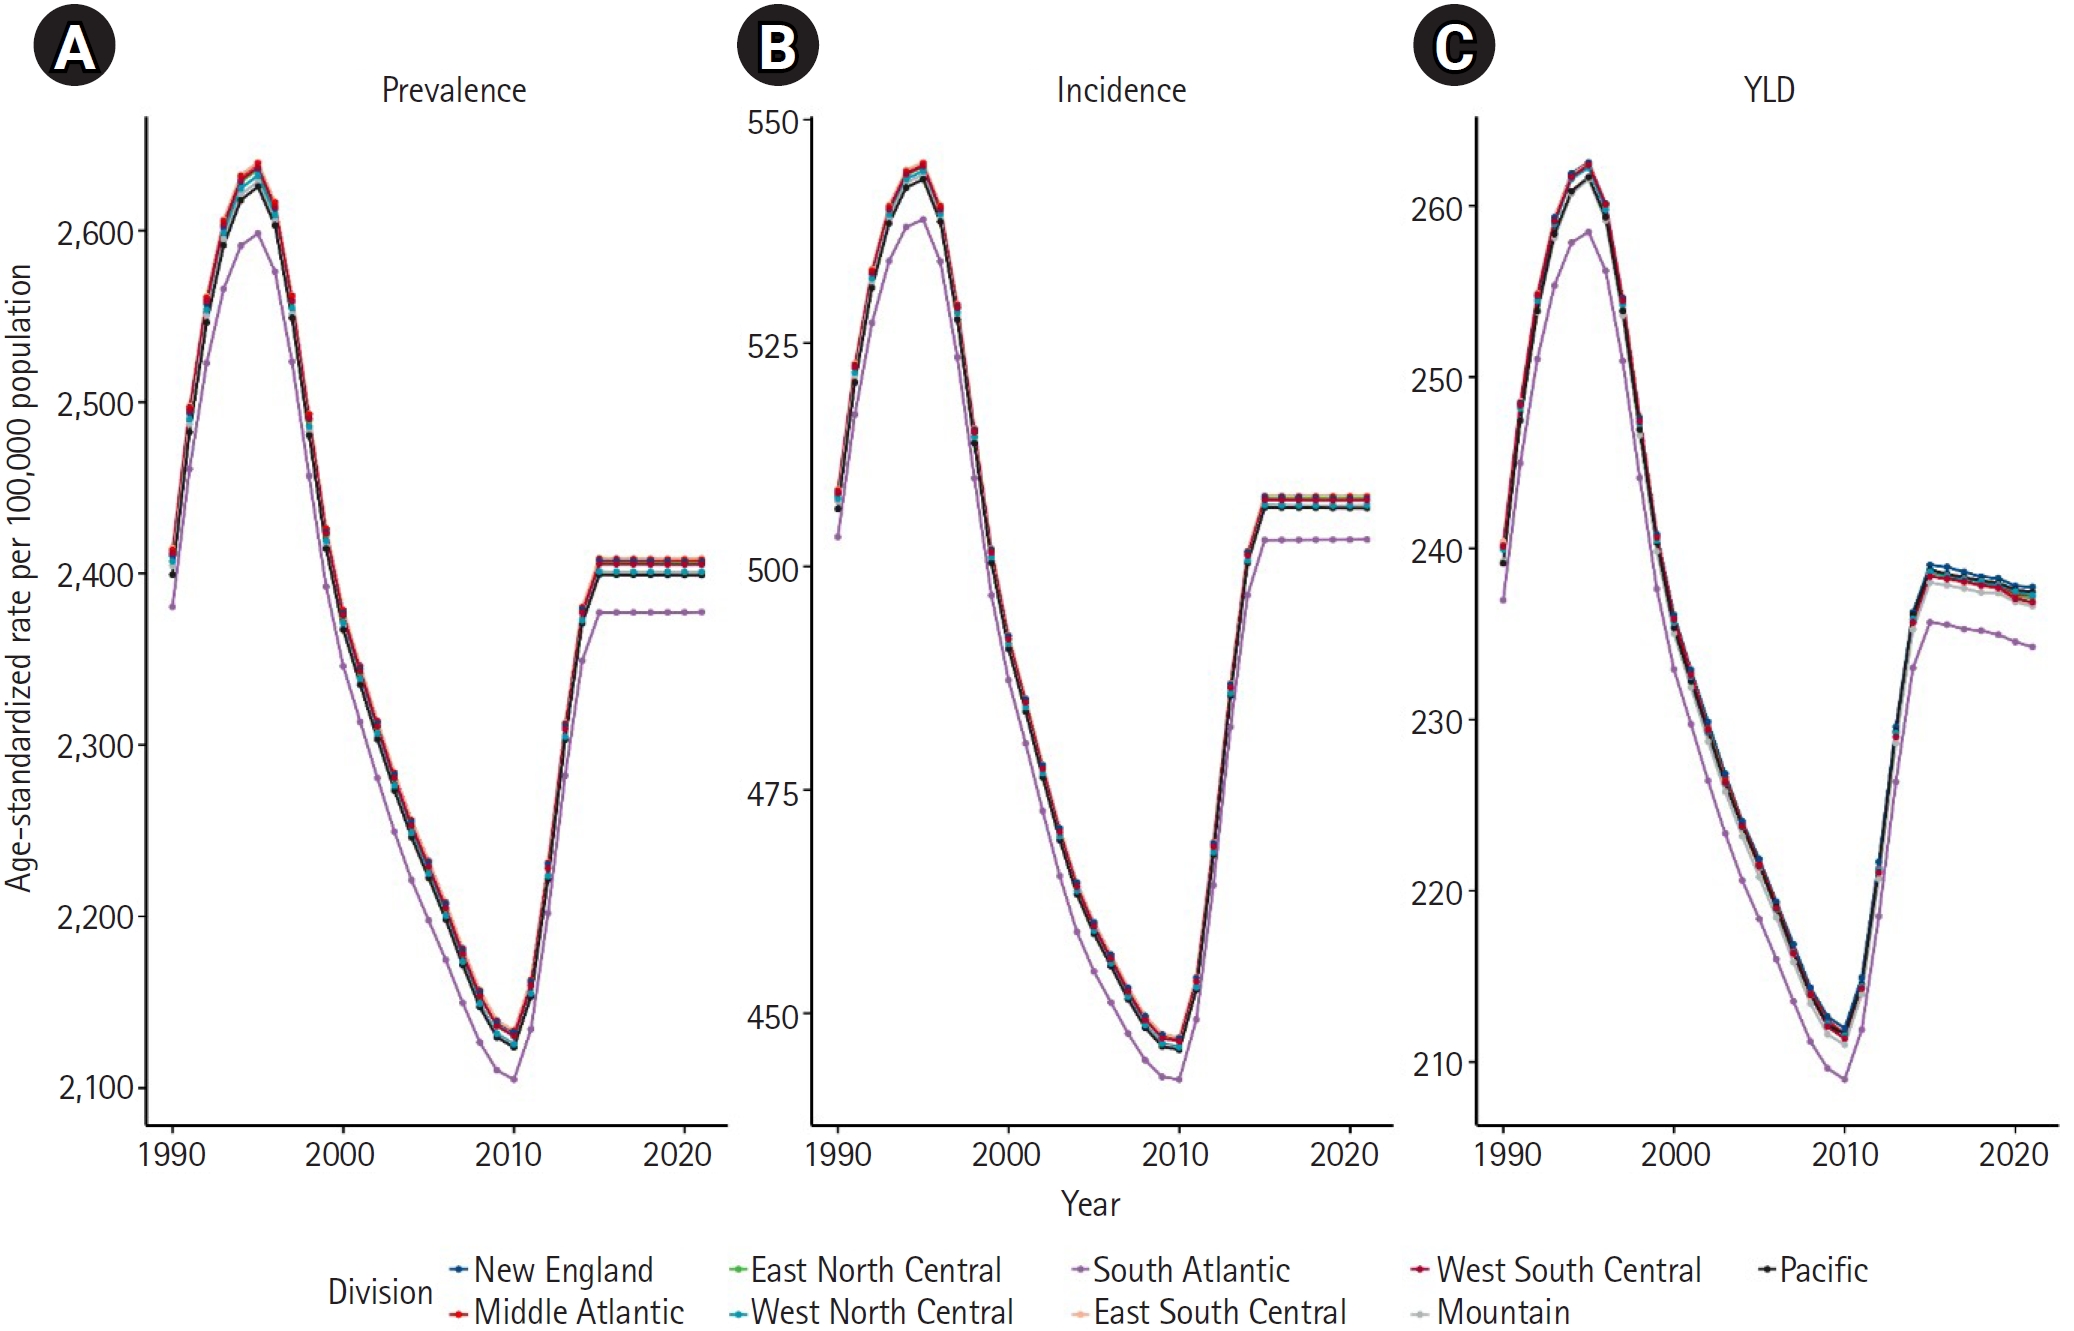
Fig. 3.(A, B) Counts and age-standardized prevalence and years lived with disability (YLD) rates for neck pain by sex in the United States, 1990–2021. Age-standardized prevalence and YLD rates declined slightly over the study period despite overall increases in absolute counts. Females had higher prevalence and YLD rates and absolute counts than males throughout the study period.
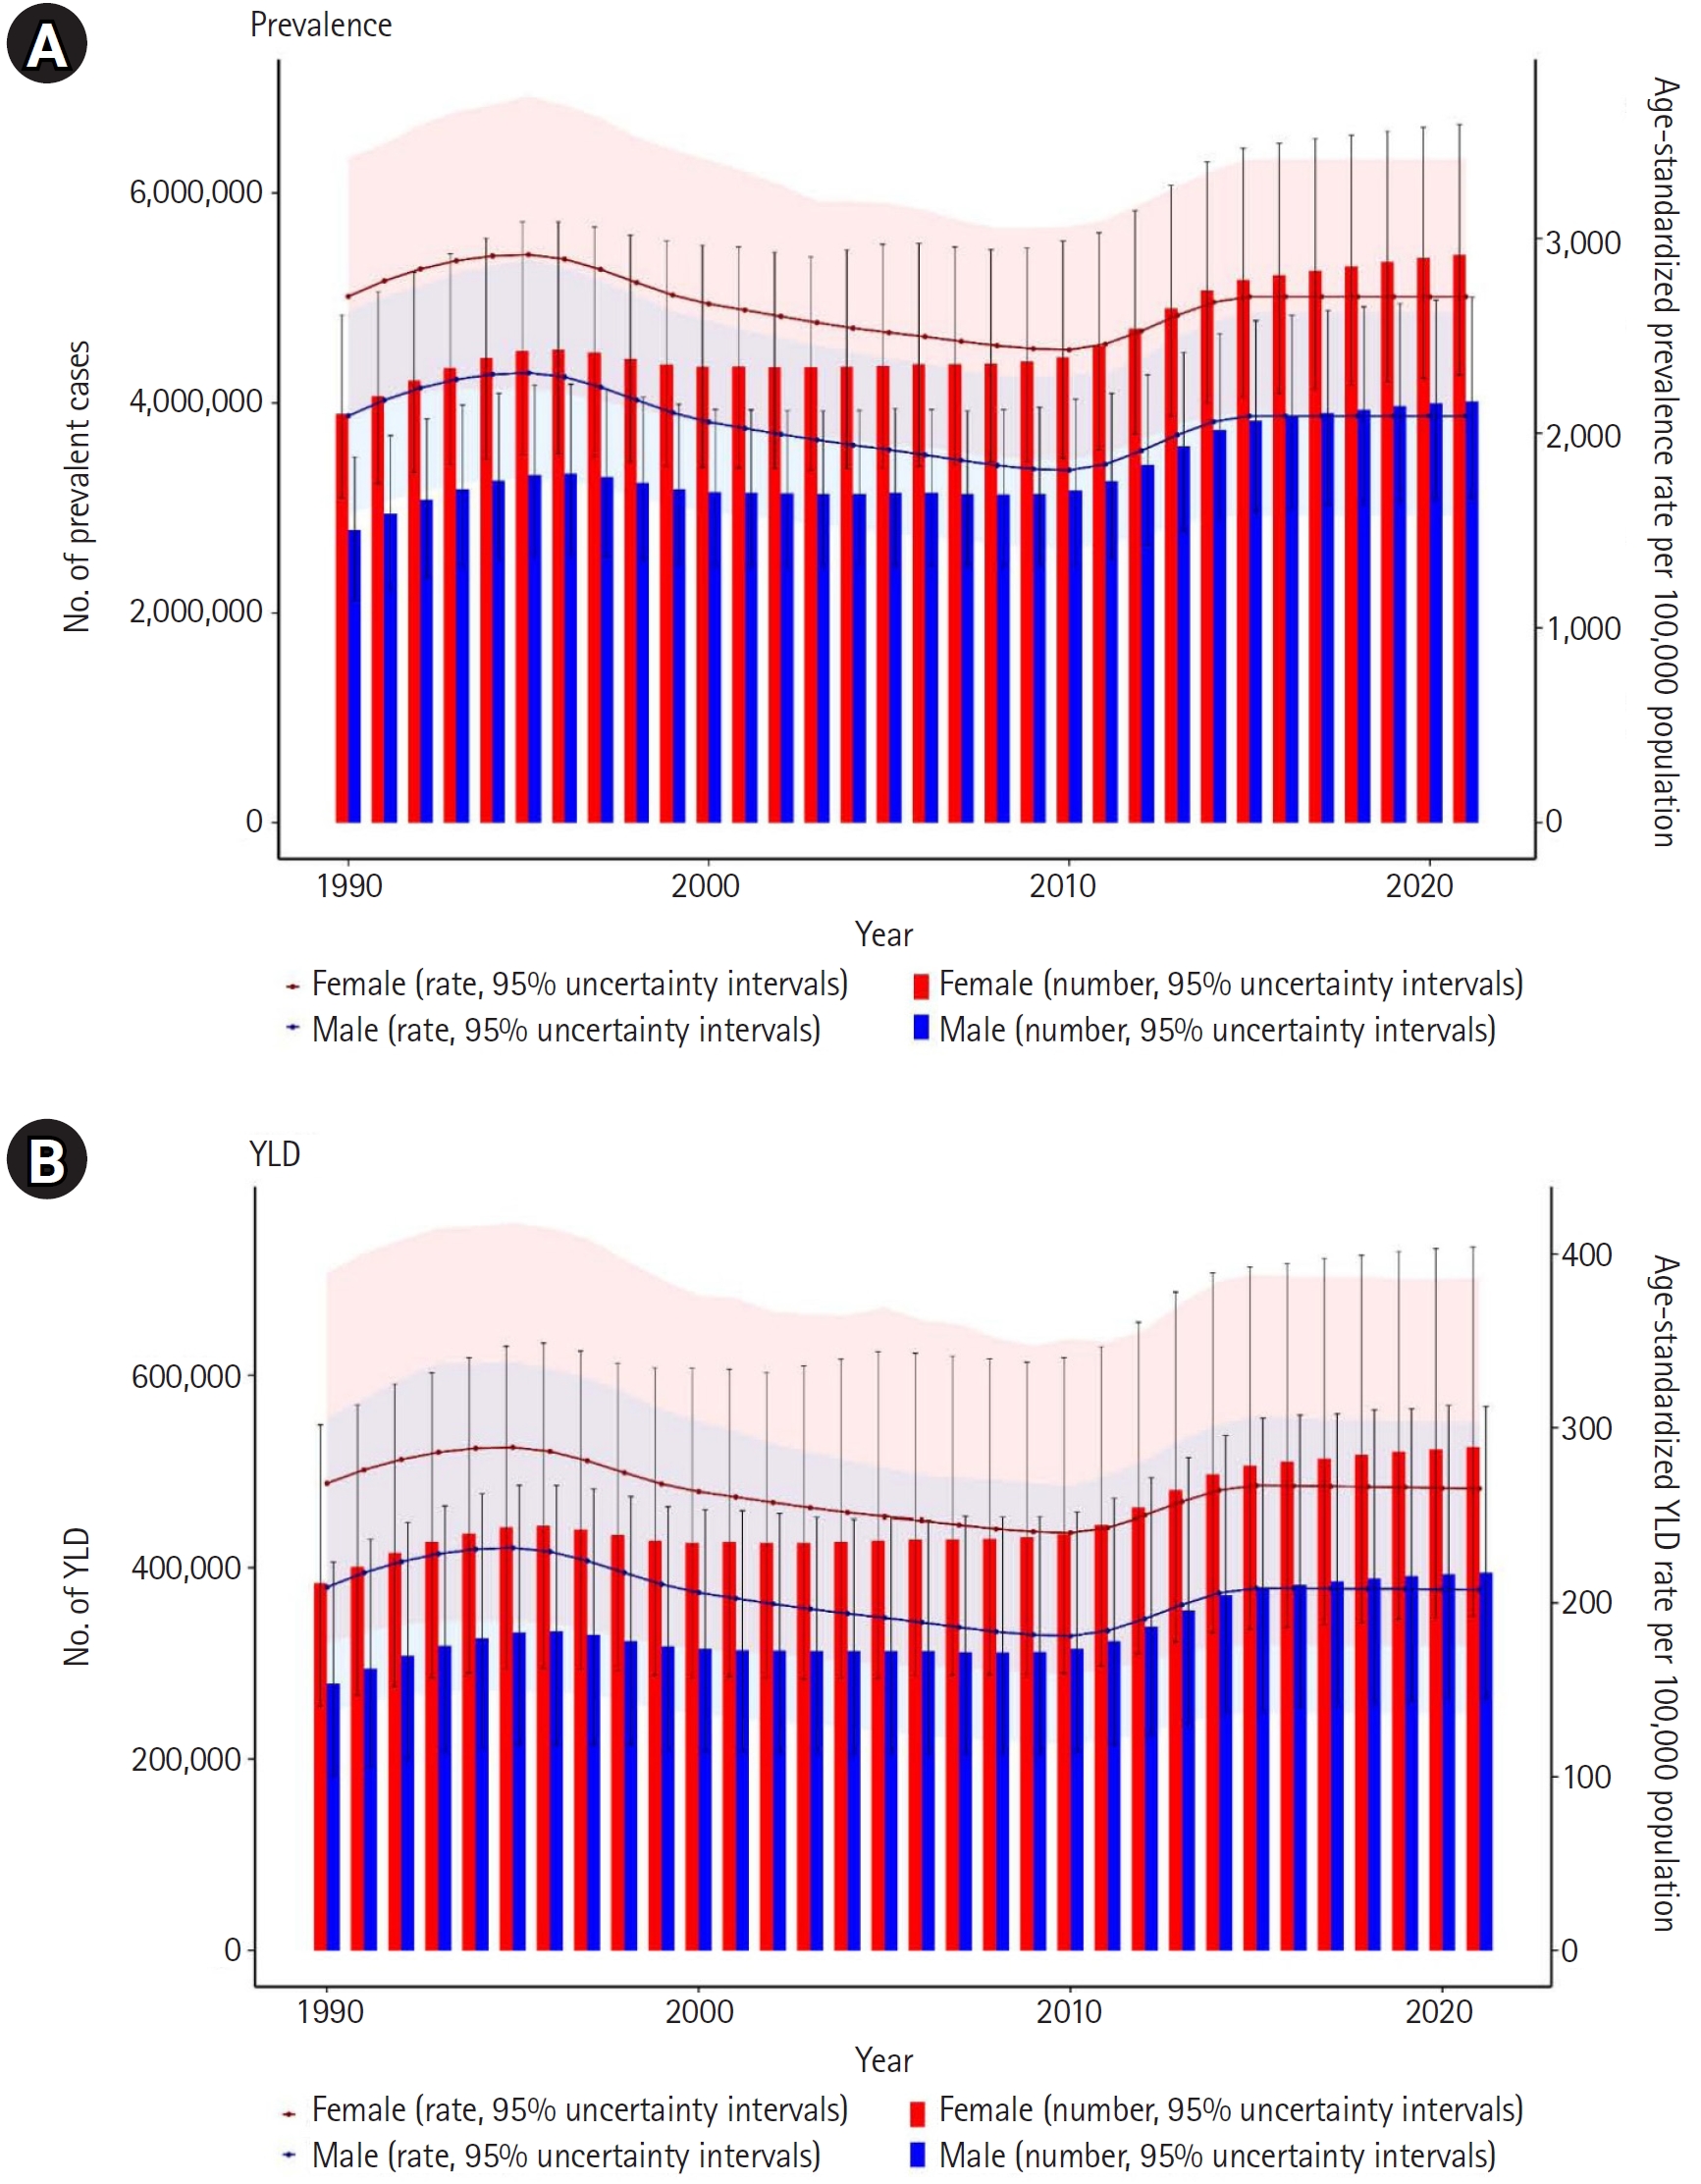
Fig. 4.(A, B) Counts and age-standardized prevalence and years lived with disability (YLD) rates for neck pain by age group and sex in the United States, 2021. Prevalence and YLD rates peaked in middle age in both sexes. Females had notably higher prevalence and YLD rates than males in most age groups.
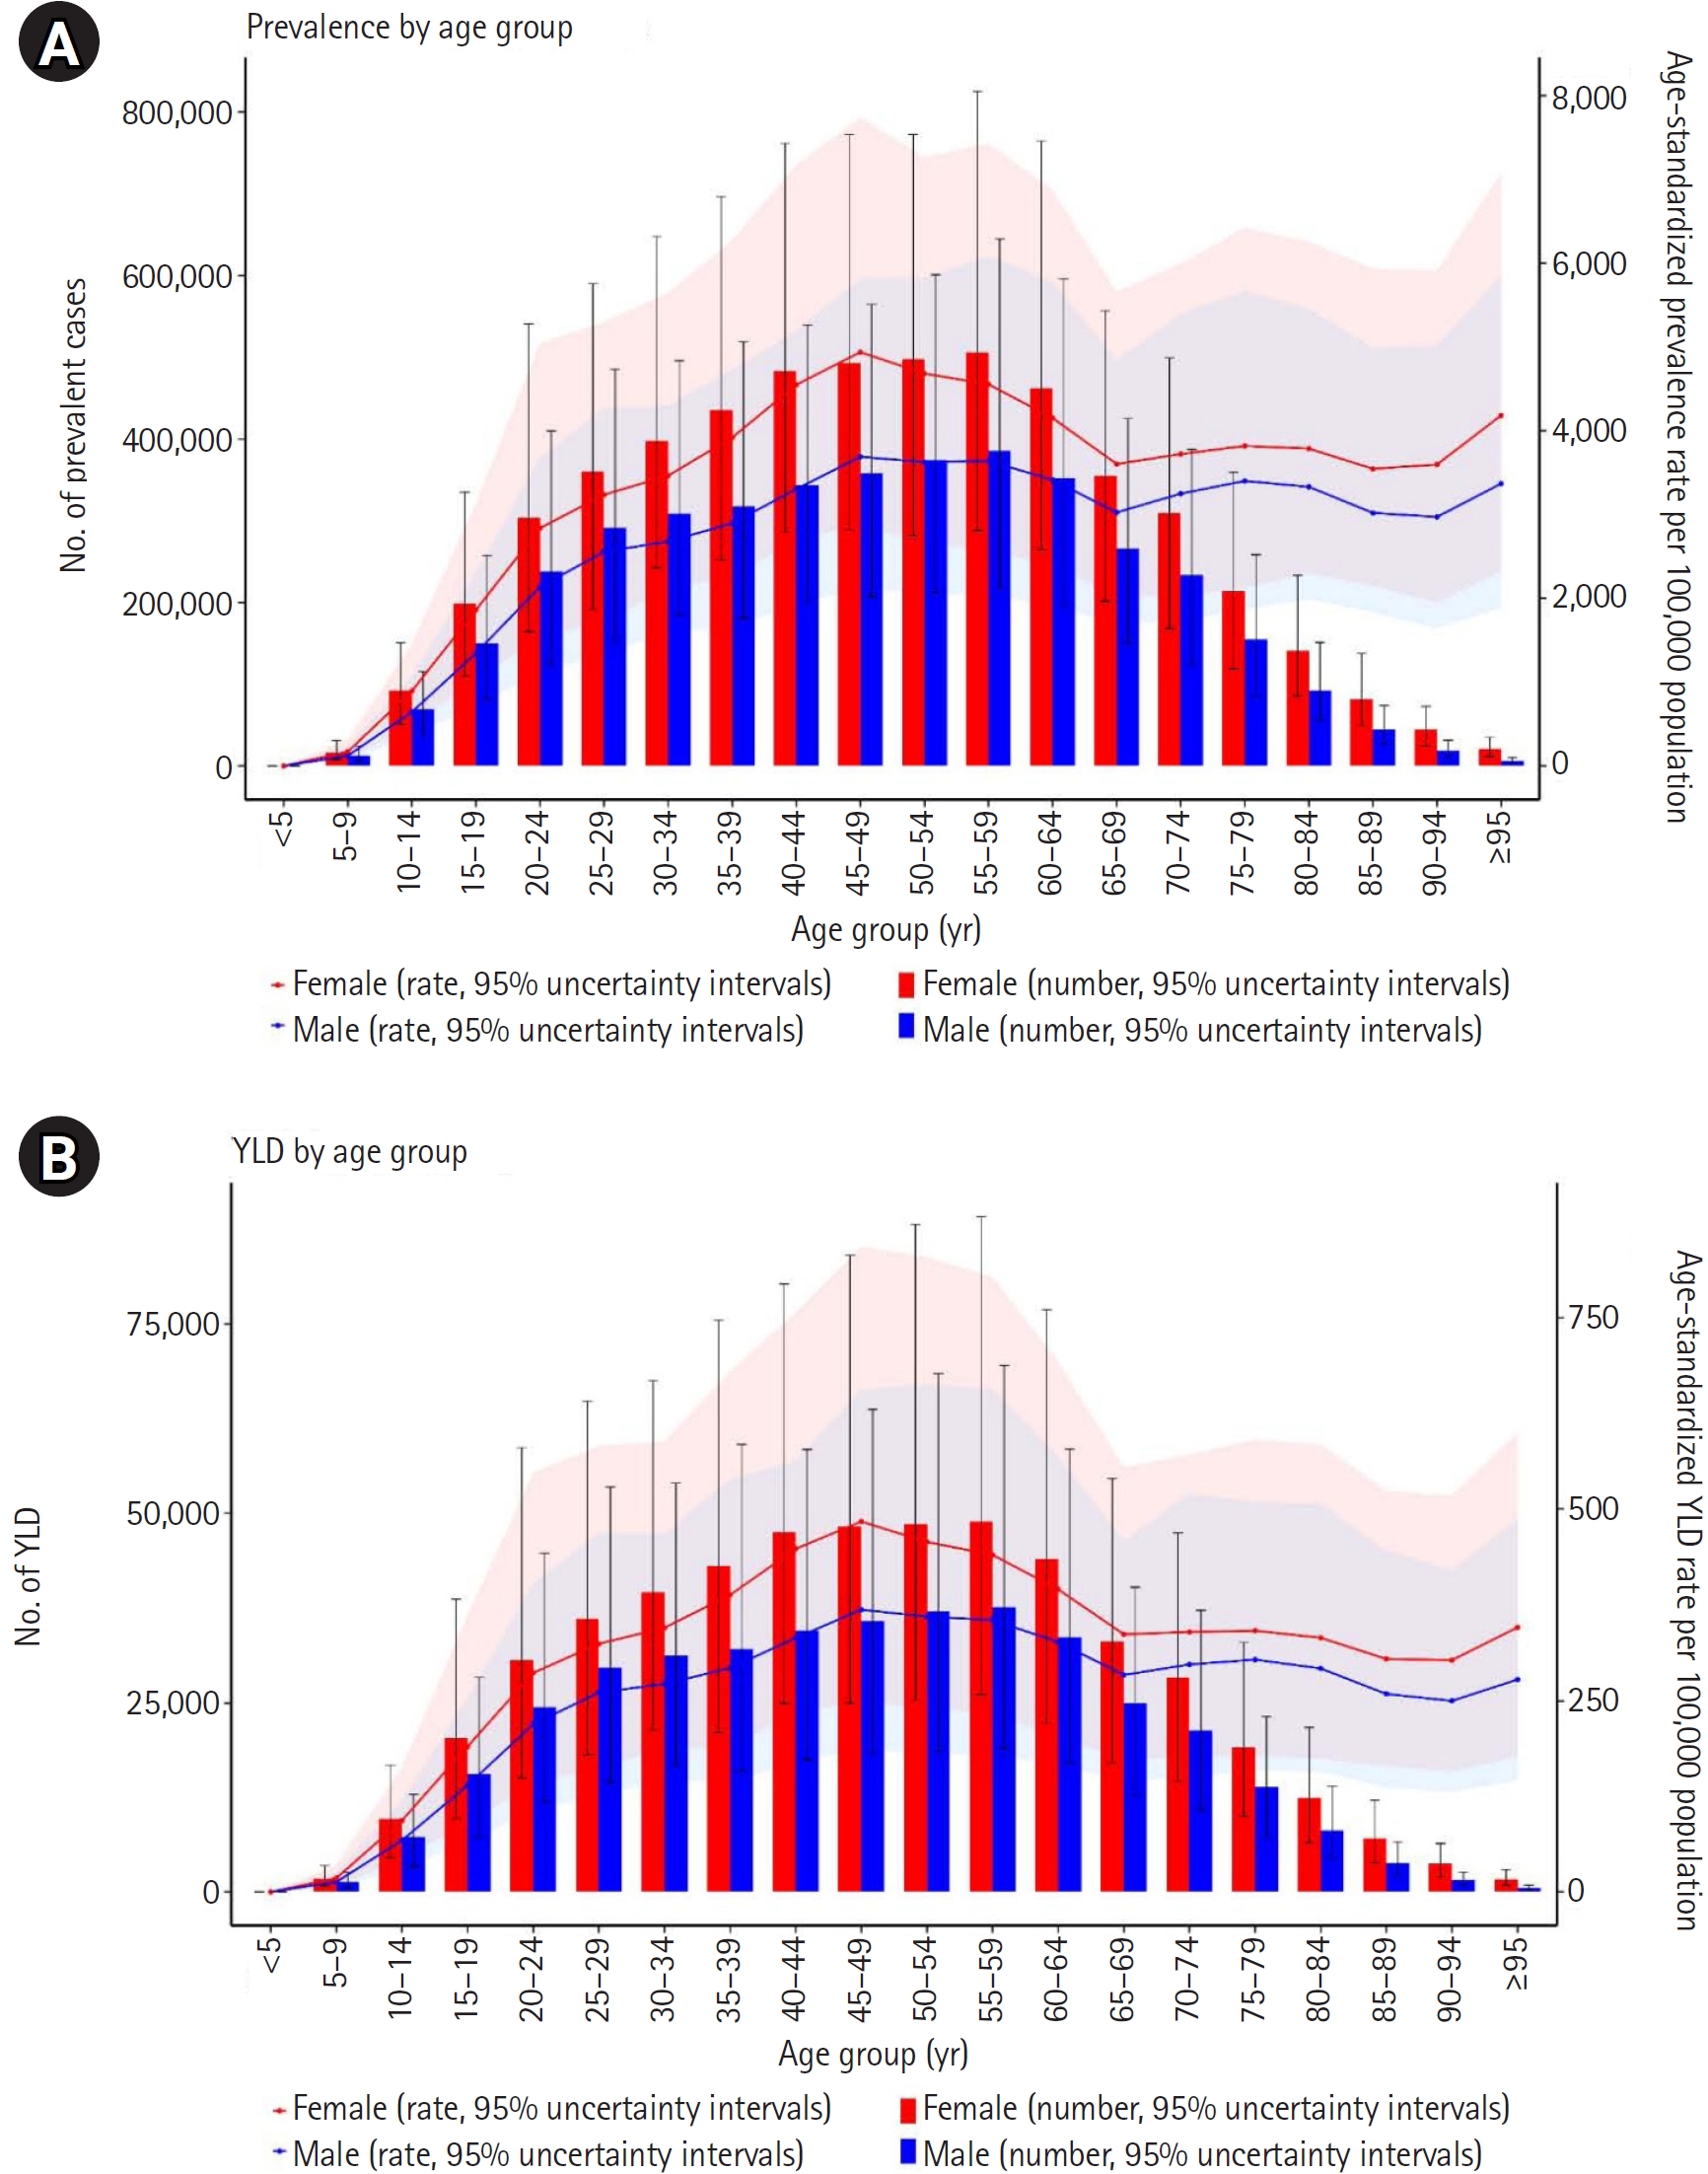
Table 1.Counts, age-standardized rates, and percentage changes in neck pain prevalence, incidence, and years lived with disability in the United States
|
Prevalence (95% UI) |
Incidence (95% UI) |
YLD (95% UI) |
|
Absolute no., 2021 |
Age-standardized rate, per 100,000 people, 2021 |
Percentage change, 1990–2021 |
Absolute no., 2021 |
Age-standardized rate, per 100,000 people, 2021 |
Percentage change, 1990–2021 |
Absolute no., 2021 |
Age-standardized rate, per 100,000 people, 2021 |
Percentage change, 1990–2021 |
|
USA |
9,430,459.08 |
2,397.27 |
−0.20% |
1,904,357.69 |
506.12 |
−0.11% |
919,636.54 |
236.52 |
−1.12% |
|
(7,397,000.55–11,590,635.22) |
(1,850.62–3,002.28) |
(−0.32 to −0.10) |
(1,493,203.04–2,320,318.77) |
(397.88–614.23) |
(−0.18 to −0.06) |
(618,463.09–1,301,733.09) |
(157.55–342.46) |
(−2.02 to −0.22) |
|
Region |
|
|
|
|
|
|
|
|
|
|
Northeast |
1,675,676.96 |
2,408.33 |
−0.18% |
335,417.46 |
507.81 |
−0.12% |
163,018.71 |
237.41 |
−1.06% |
|
(1,316,537.01–2,061,505.89) |
(1,861.49–3,014.08) |
(−0.30 to −0.07) |
(263,128.49–409,032.00) |
(399.14–615.64) |
(−0.21 to −0.04) |
(109,213.79–229,215.27) |
(157.42–342.62) |
(−3.83 to 1.80) |
|
Midwest |
1,956,325.46 |
2,405.47 |
−0.24% |
394,564.61 |
507.47 |
−0.14% |
190,554.02 |
237.27 |
−1.17% |
|
(1,538,182.37–2,402,797.79) |
(1,859.10–3,009.82) |
(−0.35 to −0.12) |
(309,652.40–480,065.65) |
(398.92–615.17) |
(−0.21 to −0.07) |
(127,942.42–270,069.38) |
(157.31–343.48) |
(−4.01 to 1.74) |
|
South |
3,561,588.44 |
2,384.03 |
−0.19% |
721,483.72 |
504.01 |
−0.10% |
347,089.90 |
234.97 |
−1.29% |
|
(2,789,143.50–4,397,409.95) |
(1,836.53–2,990.02) |
(−0.32 to −0.07) |
(565,325.60–879,466.55) |
(395.38–612.84) |
(−0.19 to −0.02) |
(231,787.61–492,812.36) |
(155.18–340.66) |
(−4.14 to 1.70) |
|
West |
2,236,868.21 |
2,403.17 |
−0.10% |
452,891.89 |
507.09 |
−0.05% |
218,973.92 |
237.65 |
−0.95% |
|
(1,760,241.06–2,761,260.99) |
(1,857.14–3,006.66) |
(−0.20 to 0.00) |
(356,008.45–550,939.96) |
(398.65–614.72) |
(−0.13 to 0.03) |
(147,594.07–310,862.07) |
(159.08–344.34) |
(−3.79 to 1.97) |
|
Division |
|
|
|
|
|
|
|
|
|
|
New England |
446,118.20 |
2,408.26 |
−0.16% |
88,997.35 |
507.81 |
−0.11% |
43,498.57 |
238.03 |
−0.98% |
|
(349,872.16–548,393.47) |
(1,861.34–3,014.12) |
(−0.27 to −0.04) |
(69,904.71–108,752.82) |
(399.15–615.63) |
(−0.20 to −0.03) |
(29,183.10–61,117.65) |
(158.38–342.23) |
(−3.77 to 1.96) |
|
South Atlantic |
1,880,004.62 |
2,363.83 |
−0.12% |
379,830.73 |
500.77 |
−0.05% |
182,934.78 |
233.00 |
−1.15% |
|
(1,466,755.24–2,324,278.74) |
(1,815.53–2,970.66) |
(−0.25 to −0.01) |
(297,155.67–464,279.89) |
(392.13–610.55) |
(−0.15 to 0.03) |
(122,054.19–258,992.69) |
(153.18–337.40) |
(−3.98 to 1.84) |
|
East South Central |
550,630.53 |
2,409.01 |
−0.25% |
111,071.93 |
507.95 |
−0.14% |
53,453.54 |
236.63 |
−1.53% |
|
(433,315.46–676,597.74) |
(1,862.14–3,014.77) |
(−0.37 to −0.13) |
(87,024.04–135,385.45) |
(399.26–615.80) |
(−0.22 to −0.07) |
(35,784.91–75,340.44) |
(157.15–343.20) |
(−4.55 to 1.52) |
|
West South Central |
1,130,953.32 |
2,406.06 |
−0.28% |
230,581.07 |
507.51 |
−0.16% |
110,701.58 |
237.48 |
−1.36% |
|
(889,072.82–1,396,533.49) |
(1,859.60–3,010.74) |
(−0.40 to −0.15) |
(181,145.90–279,801.21) |
(398.94–615.25) |
(−0.25 to −0.09) |
(73,948.51–158,479.23) |
(157.60–344.93) |
(−4.08 to 1.54) |
|
State |
|
|
|
|
|
|
|
|
|
|
District of Columbia |
20,434.58 |
2,418.69 |
−0.18% |
4,104.72 |
509.91 |
0.01% |
2,011.58 |
239.24 |
−0.76% |
|
(15,781.24–25,472.37) |
(1,872.06–3,028.00) |
(−0.42 to 0.03) |
(3,187.07–5,143.15) |
(400.68–618.27) |
(−0.16 to 0.17) |
(1,333.48–2,887.79) |
(158.86–344.07) |
(−3.61 to 2.09) |
|
Georgia |
304,380.90 |
2,414.23 |
0.04% |
61,579.98 |
508.73 |
0.06% |
29,756.29 |
238.18 |
−0.82% |
|
(239,793.30–375,891.13) |
(1,866.65–3,022.25) |
(−0.09 to 0.15) |
(48,296.90–75,022.28) |
(399.78–616.77) |
(−0.06 to 0.16) |
(19,990.54–42,326.97) |
(157.67–341.69) |
(−3.66 to 2.11) |
|
Delaware |
28,839.58 |
2,411.57 |
−0.05% |
5,786.30 |
508.22 |
−0.06% |
2,796.42 |
237.28 |
−1.06% |
|
(22,731.33–35,324.88) |
(1,863.91–3,019.02) |
(−0.13 to 0.03) |
(4,541.04–7,051.12) |
(399.47–616.16) |
(−0.13 to 0.01) |
(1,876.34–3,947.11) |
(156.90–341.21) |
(−4.02 to 1.87) |
|
North Carolina |
262,446.99 |
2,117.28 |
0.02% |
54,918.22 |
462.03 |
0.06% |
25,618.37 |
209.18 |
−1.04% |
|
(194,268.32–336,478.96) |
(1,562.06–2,727.70) |
(−0.10 to 0.11) |
(41,729.13–68,088.33) |
(353.71–582.12) |
(−0.01 to 0.12) |
(16,589.14–37,278.85) |
(135.10–316.54) |
(−3.86 to 2.13) |
|
Wyoming |
16,019.06 |
2,389.95 |
−0.49% |
3,255.85 |
505.16 |
−0.34% |
1,560.11 |
235.46 |
−1.53% |
|
(12,584.79–19,607.87) |
(1,845.52–2,987.94) |
(−0.68 to −0.31) |
(2,566.95–3,967.72) |
(397.29–612.28) |
(−0.49 to −0.21) |
(1,056.88–2,182.99) |
(157.69–337.86) |
(−4.20 to 1.28) |
|
West Virginia |
51,882.55 |
2,401.68 |
−0.47% |
10,388.75 |
506.90 |
−0.29% |
4,988.65 |
234.68 |
−2.18% |
|
(40,813.57–63,557.33) |
(1,855.75–3,004.27) |
(−0.66 to −0.29) |
(8,197.09–12,701.63) |
(398.53–614.46) |
(−0.42 to −0.17) |
(3,378.14–6,976.26) |
(156.67–338.49) |
(−5.05 to 0.85) |
|
Louisiana |
129,281.67 |
2,405.46 |
−0.44% |
26,195.50 |
507.41 |
−0.28% |
12,574.41 |
236.49 |
−1.52% |
|
(101,436.09–158,870.70) |
(1,859.22–3,009.90) |
(−0.61 to −0.27) |
(20,573.18–31,915.60) |
(398.88–615.12) |
(−0.39 to −0.18) |
(8,444.69–17,733.97) |
(157.65–342.28) |
(−4.29 to 1.25) |
|
Nevada |
89,378.85 |
2,402.00 |
0.22% |
18,068.06 |
507.07 |
0.15% |
8,721.49 |
236.61 |
−0.75% |
|
(70,428.82–110,592.38) |
(1,856.35–3,004.92) |
(0.13 to 0.32) |
(14,201.51–21,991.34) |
(398.65–614.61) |
(0.06 to 0.23) |
(5,886.57–12,374.48) |
(159.03–341.18) |
(−3.68 to 2.38) |
References
- 1. Hogg-Johnson S, van der Velde G, Carroll LJ, Holm LW, Cassidy JD, Guzman J, Côté P, Haldeman S, Ammendolia C, Carragee E, Hurwitz E, Nordin M, Peloso P; Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders. The burden and determinants of neck pain in the general population: results of the Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders. Spine (Phila Pa 1976) 2008;33(4 Suppl):S39-S51. https://doi.org/10.1097/BRS.0b013e31816454c8
- 2. Safiri S, Kolahi AA, Hoy D, Buchbinder R, Mansournia MA, Bettampadi D, Ashrafi-Asgarabad A, Almasi-Hashiani A, Smith E, Sepidarkish M, Cross M, Qorbani M, Moradi-Lakeh M, Woolf AD, March L, Collins G, Ferreira ML. Global, regional, and national burden of neck pain in the general population, 1990-2017: systematic analysis of the Global Burden of Disease Study 2017. BMJ 2020;368:m791. https://doi.org/10.1136/bmj.m791
- 3. United States Bone and Joint Initiative. The burden of musculoskeletal diseases in the United States (BMUS). 4th ed. United States Bone and Joint Initiative; 2020.
- 4. Kazeminasab S, Nejadghaderi SA, Amiri P, Pourfathi H, Araj-Khodaei M, Sullman MJM, Kolahi AA, Safiri S. Neck pain: global epidemiology, trends and risk factors. BMC Musculoskelet Disord 2022;23:26. https://doi.org/10.1186/s12891-021-04957-4
- 5. Dieleman JL, Cao J, Chapin A, Chen C, Li Z, Liu A, Horst C, Kaldjian A, Matyasz T, Scott KW, Bui AL, Campbell M, Duber HC, Dunn AC, Flaxman AD, Fitzmaurice C, Naghavi M, Sadat N, Shieh P, Squires E, Yeung K, Murray CJL. US health care spending by payer and health condition, 1996-2016. JAMA 2020;323:863-884. https://doi.org/10.1001/jama.2020.0734
- 6. Stewart WF, Ricci JA, Chee E, Morganstein D, Lipton R. Lost productive time and cost due to common pain conditions in the US workforce. JAMA 2003;290:2443-2454. https://doi.org/10.1001/jama.290.18.2443
- 7. GBD 2021 Neck Pain Collaborators. Global, regional, and national burden of neck pain, 1990-2020, and projections to 2050: a systematic analysis of the Global Burden of Disease Study 2021. Lancet Rheumatol 2024;6:e142-e155. https://doi.org/10.1016/S2665-9913(23)00321-1
- 8. GBD 2021 US Burden of Disease Collaborators. The burden of diseases, injuries, and risk factors by state in the USA, 1990-2021: a systematic analysis for the Global Burden of Disease Study 2021. Lancet 2024;404:2314-2340. https://doi.org/10.1016/S0140-6736(24)01446-6
- 9. Global Burden of Disease Collaborative Network. Global Burden of Disease Study 2021 (GBD 2021). Institute for Health Metrics and Evaluation; 2024.
- 10. GBD 2021 Diseases and Injuries Collaborators. Global incidence, prevalence, years lived with disability (YLDs), disability-adjusted life-years (DALYs), and healthy life expectancy (HALE) for 371 diseases and injuries in 204 countries and territories and 811 subnational locations, 1990-2021: a systematic analysis for the Global Burden of Disease Study 2021. Lancet 2024;403:2133-2161. https://doi.org/10.1016/S0140-6736(24)00757-8
- 11. Zajacova A, Lee J, Grol-Prokopczyk H. The geography of pain in the United States and Canada. J Pain 2022;23:2155-2166. https://doi.org/10.1016/j.jpain.2022.08.002
- 12. Zajacova A, Grol-Prokopczyk H, Zimmer Z. Pain trends among American Adults, 2002-2018: patterns, disparities, and correlates. Demography 2021;58:711-738. https://doi.org/10.1215/00703370-8977691
- 13. Cheng S, Cao J, Hou L, Li S, Sun W, Shan S, Zhao J, Yao L, Li X, He B, Song P. Temporal trends and projections in the global burden of neck pain: findings from the Global Burden of Disease Study 2019. Pain 2024;165:2804-2813. https://doi.org/10.1097/j.pain.0000000000003298
- 14. Menendez ME, Moverman MA, Moon AS, Ring D. State-level Google search volumes for neck and shoulder pain correlate with psychosocial and behavioral health indicators. J Natl Med Assoc 2021;113:522-527. https://doi.org/10.1016/j.jnma.2021.04.001
- 15. Stevens GA, Alkema L, Black RE, Boerma JT, Collins GS, Ezzati M, Grove JT, Hogan DR, Hogan MC, Horton R, Lawn JE, Marušić A, Mathers CD, Murray CJ, Rudan I, Salomon JA, Simpson PJ, Vos T, Welch V; (The GATHER Working Group). Guidelines for Accurate and Transparent Health Estimates Reporting: the GATHER statement. Lancet 2016;388:e19-e23. https://doi.org/10.1016/S0140-6736(16)30388-9
- 16. GBD 2013 Mortality and Causes of Death Collaborators. Global, regional, and national age-sex specific all-cause and cause-specific mortality for 240 causes of death, 1990-2013: a systematic analysis for the Global Burden of Disease Study 2013. Lancet 2015;385:117-171. https://doi.org/10.1016/S0140-6736(14)61682-2
- 17. Zimmer Z, Rubin S. Life expectancy with and without pain in the U.S. elderly population. J Gerontol A Biol Sci Med Sci 2016;71:1171-1176. https://doi.org/10.1093/gerona/glw028
- 18. GBD 2021 Other Musculoskeletal Disorders Collaborators. Global, regional, and national burden of other musculoskeletal disorders, 1990-2020, and projections to 2050: a systematic analysis of the Global Burden of Disease Study 2021. Lancet Rheumatol 2023;5:e670-e682. https://doi.org/10.1016/S2665-9913(23)00232-1
- 19. Tsui J, Hirsch JA, Bayer FJ, Quinn JW, Cahill J, Siscovick D, Lovasi GS. Patterns in geographic access to health care facilities across neighborhoods in the United States based on data from the national establishment time-series between 2000 and 2014. JAMA Netw Open 2020;3:e205105. https://doi.org/10.1001/jamanetworkopen.2020.5105
- 20. Salazar DH, Dy CJ, Choate WS, Place HM. Disparities in access to musculoskeletal care: narrowing the gap: AOA Critical Issues Symposium. J Bone Joint Surg Am 2019;101:e121. https://doi.org/10.2106/JBJS.18.01106
- 21. Hoy D, March L, Woolf A, Blyth F, Brooks P, Smith E, Vos T, Barendregt J, Blore J, Murray C, Burstein R, Buchbinder R. The global burden of neck pain: estimates from the global burden of disease 2010 study. Ann Rheum Dis 2014;73:1309-1315. https://doi.org/10.1136/annrheumdis-2013-204431
- 22. Shin DW, Shin JI, Koyanagi A, Jacob L, Smith L, Lee H, Chang Y, Song TJ. Global, regional, and national neck pain burden in the general population, 1990-2019: an analysis of the global burden of disease study 2019. Front Neurol 2022;13:955367. https://doi.org/10.3389/fneur.2022.955367
- 23. McLean SM, May S, Klaber-Moffett J, Sharp DM, Gardiner E. Risk factors for the onset of non-specific neck pain: a systematic review. J Epidemiol Community Health 2010;64:565-572. https://doi.org/10.1136/jech.2009.090720
- 24. Côté P, van der Velde G, Cassidy JD, Carroll LJ, Hogg-Johnson S, Holm LW, Carragee EJ, Haldeman S, Nordin M, Hurwitz EL, Guzman J, Peloso PM; Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders. The burden and determinants of neck pain in workers: results of the Bone and Joint Decade 2000-2010 Task Force on Neck Pain and Its Associated Disorders. Spine (Phila Pa 1976) 2008;33(4 Suppl):S60-S74. https://doi.org/10.1097/BRS.0b013e3181643ee4
- 25. Gibbons MM, Taylor AL, Brown E, Daniels SK, Hardin EE, Manring S. Assessing postsecondary barriers for rural Appalachian high school students. J Career Assess 2020;28:165-181. https://doi.org/10.1177/1069072719845329
- 26. Chetty R, Stepner M, Abraham S, Lin S, Scuderi B, Turner N, Bergeron A, Cutler D. The association between income and life expectancy in the United States, 2001-2014. JAMA 2016;315:1750-1766. https://doi.org/10.1001/jama.2016.4226
- 27. Hey HWD, Lim JXY, Ong JZ, Luo N. Epidemiology of neck pain and its impact on quality-of-life-a population-based, cross sectional study in Singapore. Spine (Phila Pa 1976) 2021;46:1572-1580. https://doi.org/10.1097/BRS.0000000000004071
- 28. Stemper BD, Yoganandan N, Pintar FA. Gender- and region-dependent local facet joint kinematics in rear impact: implications in whiplash injury. Spine (Phila Pa 1976) 2004;29:1764-1771. https://doi.org/10.1097/01.brs.0000134563.10718.a7
- 29. Vincent K, Warnaby C, Stagg CJ, Moore J, Kennedy S, Tracey I. Brain imaging reveals that engagement of descending inhibitory pain pathways in healthy women in a low endogenous estradiol state varies with testosterone. Pain 2013;154:515-524. https://doi.org/10.1016/j.pain.2012.11.016
- 30. McLean CP, Anderson ER. Brave men and timid women?: a review of the gender differences in fear and anxiety. Clin Psychol Rev 2009;29:496-505. https://doi.org/10.1016/j.cpr.2009.05.003
- 31. Strine TW, Hootman JM. US national prevalence and correlates of low back and neck pain among adults. Arthritis Rheum 2007;57:656-665. https://doi.org/10.1002/art.22684
- 32. Hu S, Huang Y, Hu Y, Zhang W, Wang S, Dong Y. Burden, trends and health inequality of early-onset neck pain in young and middle-aged adults from 1990 to 2021 with projections to 2040. SSRN [Preprint] 2025;Jul 10. https://doi.org/10.2139/ssrn.5345104
- 33. Ahangar-Sirous R, Alizadeh M, Nejadghaderi SA, Noori M, Khabbazi A, Sullman MJM, Kolahi AA, Collins GS, Safiri S. The burden of neck pain in the Middle East and North Africa region, 1990-2019. Heliyon 2023;9:e21296. https://doi.org/10.1016/j.heliyon.2023.e21296
- 34. Rikard SM, Strahan AE, Schmit KM, Guy GP. Chronic pain among adults: United States, 2019-2021. MMWR Morb Mortal Wkly Rep 2023;72:379-385. https://doi.org/10.15585/mmwr.mm7215a1
- 35. Lucas JW, Connor EM, Bose J. Back, lower limb, and upper limb pain among U.S. adults, 2019. NCHS Data Brief 2021;(415):1-8. https://doi.org/10.15620/cdc:107894
- 36. Institute of Medicine (US) Committee on Advancing Pain Research, Care, and Education. Relieving pain in America: a blueprint for transforming prevention, care, education, and research. National Academies Press (US); 2011. https://doi.org/10.17226/13172
- 37. Paksaichol A, Janwantanakul P, Purepong N, Pensri P, van der Beek AJ. Office workers’ risk factors for the development of non-specific neck pain: a systematic review of prospective cohort studies. Occup Environ Med 2012;69:610-618. https://doi.org/10.1136/oemed-2011-100459
- 38. Bevan S, Quadrello T, McGee R, European M, Vavrovsky A, Barham L. Fit for work?: musculoskeletal disorders in the European workforce. The Work Foundation; 2009.


 , Dong Woo Shin2